Wednesday, May 03, 2017

Shaanxi Province Announces Their 1st H7N9 Case


#12,426


This 5th H7N9 epidemic (starting in October 2016) has been a season of `firsts', with the virus splitting into two distinct lineages (Pearl River Delta & Yangtze River Delta),  the emergence of an HPAI version of the virus in Guangdong Province, and as we discussed yesterday, the spread of the virus to 5 previously unaffected regions (3 provinces, 2 municipalities) on the Mainland (plus Macao).
Today we can add a sixth region on the Mainland, as overnight Sharon Sanders of FluTrackers picked up a media & government report on the first case from Shaanxi Province.

The patient, a 62 y.o. male, was hospitalized with fever and severe respiratory symptoms in Xianyang City (pop. 5 million)  on April 23rd, but wasn't tested for the H7N9 virus for a week. The patient died on May 1st. 
The announcement from the Shaanxi government website details their emergency response, which includes the closing of urban and suburban live markets, the screening of influenza-like cases, and additional training for medical personnel. 

The official statement from the Shaanxi Health and Family Planning Commission follows.

Province confirmed one case of H7N9 cases
Time: 2017-5-3
 May 3, 2017, the province confirmed 1 case of H7N9 cases.

    Patient Zhang, male, 62 years old. Who lives in Xianyang City, Qindu District, patients on April 23, 2017 due to intermittent fever, cough for 5 days, admitted to the First Hospital of Xianyang City, Department of Respiratory Medicine, April 25 due to exacerbation of illness transferred to the Second Affiliated Hospital of ICU intensive care unit, admission diagnosis : Severe pneumonia, respiratory failure, acute myocardial ischemia, coronary heart disease, arrhythmia, hypertension 3, the course of treatment in patients with progressive disease.
April 30, the Second Affiliated Hospital of the National People's Congress sent to Xi'an, Shaanxi Province CDC detection, the results show H7N9 virus nucleic acid positive. May 1 12:00 patients died due to multiple organ failure, May 3 8:00, then the National Center for Disease Control and Prevention laboratory review report to confirm that the death of biological specimens for the H7N9 virus nucleic acid positive, the case Diagnosed as the province's first case of H7N9.

 At 7:00 on May 1, when the provincial Health and Health Committee received the report, immediately start the emergency response mechanism of sudden infectious diseases epidemic, respectively, held in Xi'an, Xianyang City, health care system and provincial H7N9 epidemic prevention joint defense joint control department meeting, research Deployment of patient treatment and epidemic prevention and control work. The provincial government attaches great importance to the deputy governor Wei Zengjun made important instructions, requiring the provincial health planning commission and the relevant city attaches great importance to go all out to do the epidemic prevention and control work to prevent the spread of the epidemic spread.
Xi'an, Xianyang municipal government immediately held a special meeting arrangements for the deployment of prevention and control work, decided to close the urban and suburban all live poultry market; all the size of the farm households to conduct investigation and thorough disinfection.
Close contact with the home medical observation, and reserve the necessary drugs, equipment, good case-related treatment preparation. Provincial Trade and Industry Bureau issued an emergency prevention and control work notice, requiring the closure of urban live poultry market, standardize the market order, strict implementation of supervision responsibilities.
Provincial Health and Health Committee to be held in the afternoon of May 3 held provincial, city, county, township four prevention and control work conference, May 4 again organized above the county medical staff to carry out influenza-like cases screening and medical treatment special training, Epidemic response and new patient treatment of the preparatory work.

 Up to now, Xi'an, Xianyang two cities and patients have had close contact with the staff have all the investigation flow finished, all medical observation of the staff were not clinical abnormalities


Tuesday, May 02, 2017

Sci Rpts:Reassorted H9N2:pH1N1 Virus Transmission After Serial Passage In Swine


#12,425


We've a new study - published today in Nature's Scientific Reports - that ticks so many of the boxes we've covered before, its hard to know where to begin. You may want to grab a fresh cup of coffee, as this may take a while.
Today's study uses the time honored technique of serial passage of a virus through a series of hosts (in this instance, pigs), to determine what host-species adaptations occur over time.
We've looked at serial passage experiments many times, most recently in a Sci Rpts study from last January H5N8 - Rapid Acquisition of Virulence Markers After Serial Passage In Mice. The concept (see graphic below) is simple. 


You inoculate a naive host with a strain of a virus, let it replicate awhile, then take the virus from the first host and inoculate a second, and then repeat the process five, ten, fifteen times or more.
Over time, the virus may better adapt to the new host (assuming there are no species barriers to prevent it).
You are simulating, in a controlled way, pretty much what goes on in the `wild' all the time. The advantage is you can compare the original virus to the downstream `adapted' virus at specific intervals to find out what genetic changes have occurred and document any behavioral changes.

The virus in today's study is a reassortment of avian H9N2  genes (HA & NA), with a backbone of internal genes from the 2009 pH1N1 virus.  

While this reassorted H9N2 virus was engineered in the laboratory, with H9N2 viruses recently reported in Chinese swine herds, circulating alongside pH1N1 virus, a naturally occurring reassortment of this type is a real possibility.

Not only does pH1N1 have a record of sharing its (already mammalian adapted) internal genes with other viruses, the H9N2 virus is very promiscuous, something we looked at in some depth just a couple of days ago (see Vet. Microb.: Analysis Of Korea Lineage Of Avian H9N2 viruses).

As the authors explain in their Introduction, previous experiments had shown limited transmissibility of H9N2 and H9N2:pH1N1 reassortants in pigs, but at levels significantly below that of swine-adapted viruses like pH1N1. The authors write (bolding mine):

In the present study, we have examined the replication and transmissibility after ten serial pig passages of a reassortant virus containing A/quail/Hong Kong/G1/1997 (H9N2) surface-protein genes and NP gene within the A/California/04/2009 (pH1N1) background to evaluate if the pH1N1 backbone confers an advantage in H9N2 adaptation to pigs.
This serial passaging of the H9N2:pH1N1 reassortant resulted in a virus that replicated in and transmitted between pigs at high rates. The predominant mutation in the passaged reassortant virus was an aspartic acid to glycine at position 225 in the HA RBS. Therefore, our results showed that the combination of reassortment and mutations induced by the serial passages generated a virus with a predominant mutation at position 225 in HA RBS that replicated and transmitted at high rates in pigs.

If a switch to glycine at position 225 in the HA gene sounds familiar, it is because it was a  source of concern during the 2009 pandemic (see Norway Reports An H1N1 Mutation), and while only rarely reported, has been linked to more severe disease.
This mutation involves an amino acid substitution at position 225 (222 using H1 Numbering) from aspartic acid (D) to glycine (G) and allows the virus to bind to receptors found deeper in the lungs, and is linked to the development of more severe pneumonia.
The development of this mutation after only 7 passages is linked to improved replication and transmission of the H9N2:pH1N1 reassortant virus in pigs. For a more detailed look at this mutation, you may wish to revisit my 2015 blog EID Journal: Emergence of D225G Variant A/H1N1, 2013–14 Flu Season, Florida.


Then entire study, while lengthy and at times complex,  is well worth reading in its entirety. I've only covered the highlights, the Abstract, and an excerpt from the discussion section follow:

A reassortant H9N2 influenza virus containing 2009 pandemic H1N1 internal-protein genes acquired enhanced pig-to-pig transmission after serial passages in swine

José Carlos Mancera Gracia, Silvie Van den Hoecke, Juergen A. Richt, Wenjun Ma, Xavier Saelens & Kristien Van Reeth
 

Scientific Reports 7, Article number: 1323 (2017)
doi:10.1038/s41598-017-01512-x
   
Received:03 February 2017
Accepted:30 March 2017
Published online:02 May 2017

Abstract

Avian H9N2 and 2009 pandemic H1N1 (pH1N1) influenza viruses can infect pigs and humans, raising the concern that H9N2:pH1N1 reassortant viruses could emerge. Such reassortants demonstrated increased replication and transmissibility in pig, but were still inefficient when compared to pH1N1. 


Here, we evaluated if a reassortant virus containing the hemagglutinin and neuraminidase of A/quail/Hong Kong/G1/1997 (H9N2) in the A/California/04/2009 (pH1N1) backbone could become better adapted to pigs by serial passaging. The tropism of the original H9N2:pH1N1 (P0) virus was restricted to the nasal mucosa, with no virus detected in the trachea or lungs.

Nevertheless, after seven passages the H9N2:pH1N1 (P7) virus replicated in the entire respiratory tract. We also compared the transmissibility of H9N2:pH1N1 (P0), H9N2:pH1N1 (P7) and pH1N1. While only 2/6 direct-contact pigs showed nasal virus excretion of H9N2:pH1N1 (P0) ≥five days, 4/6 direct-contact animals shed the H9N2:pH1N1 (P7). Interestingly, those four animals shed virus with titers similar to those of the pH1N1, which readily transmitted to all six contact animals. 

The broader tissue tropism and the increased post-transmission replication after seven passages were associated with the HA-D225G substitution. Our data demonstrate that the pH1N1 internal-protein genes together with the serial passages favour H9N2 virus adaptation to pigs.
        (SNIP)

        DISCUSSION

        (Excerpt)
In line with previous studies17, 28, this report demonstrated that avian H9N2 influenza viruses can reassort with pH1N1 internal genes, resulting in enhanced virus transmission in pigs when compared to the parental, non-reassorted H9N2 virus. The present study also underscores that repeated introduction of reassortant H9N2 viruses into the swine or humans may result in the selection of virus variants with a transmission efficiency close to that of the endemic swine or human influenza viruses.
However, the lack of transmission detected in one of the contact groups used for transmission of passage seven virus, emphasizes the complexity of the adaptation process of an avian virus to a mammalian species and the need for additional research to better understand this crucial step in cross-species transmission of influenza viruses.
         (Continue . . . )


HK CHP Avian Flu Report Week 17


#12,424


Hong Kong's Centre For Health Protection has published their latest weekly avian influenza report which details the 17 cases reported last Friday by the Mainland's NHFPC.  While a substantial drop from the previous week (n=27), this remains an elevated number for this late in the spring.
Of note, of the 24 Mainland provinces and municipalities that have reported H7N9 cases, half (n=12) have more than doubled their previous (4 year) case count, while 5 (plus Macao) have reported cases for the first time this year.

I've color coded this week's case list from Hong Kong's CHP, with yellow reflecting a doubling of cases during the past 6 months, and orange designating first time outbreaks.

Credit HK CHP - Modified with Color Coding


 Some excerpts from this week's report follows, then I'll return with a bit more.

Avian Influenza Report
 
Avian Influenza Report is a weekly report produced by the Respiratory Disease Office, Centre for Health Protection of the Department of Health. This report highlights global avian influenza activity in humans and birds.


VOLUME 13, NUMBER 17
Reporting period: April 23, 2017 – April 29, 2017 (Week 17)
(Published on May 2, 2017)


Summary

  1. Since the previous issue of Avian Influenza Report (AIR), there were 17 new human cases of avian influenza A(H7N9) reported by Mainland China health authorities in Sichuan (5 cases), Beijing (2 cases), Guangdong (2 cases) Shandong (2 cases), Chongqing (1 case), Fujian (1 case), Gansu (1 case), Henan (1 case), Hunan (1 case) and Jiangsu (1 case). Since March 2013 (as of April 29, 2017), there were a total of 1439 human cases of avian influenza A(H7N9) reported globally. Since October 2016 (as of April 29, 2017), 633 cases have been recorded in Mainland China.
  2.  Since the previous issue of AIR, there were no new human cases of avian influenza A(H5N6). Since 2014 (as of April 29, 2017), 16 human cases of avian influenza A(H5N6) were reported globally and all occurred in Mainland China. The latest case was reported on December 1, 2016.
  3. Since the previous issue of AIR, there were no new human cases of avian influenza A(H5N1). From 2011 to 2016, 10 to 145 confirmed human cases of avian influenza A(H5N1) were reported to the World Health Organization (WHO) annually (according to onset date). In 2017, there have been so far two cases in Egypt.*

               (Continue . . . .)


The age-skewing of H7N9 cases towards the elderly continues with only 1 case under the age of 40 - a four year-old girl who is listed with mild illness.   
While we've seen a smattering of children, teenagers, and young adults infected with this virus, the average age of patients has consistently stayed in the mid-to-low 50s, with younger patients usually (but not always) experiencing  milder illness. 
Whether younger people are really less likely to be infected - or simply tend to have milder illness, and are therefore less likely to be tested and counted - remains unknown.
Case counts, conditions, and outcomes provided by China only represent those patients sick enough to seek treatment at a hospital, and who are subsequently tested and correctly diagnosed. 
It is assumed that the actual number of infections likely  runs much higher, although how much higher remains the $64 question (see Beneath The H7N9 Pyramid).  

Rosselkhoznadzor: Avian Flu Infected Poultry Products Discovered In Krasnodar


#12,423


While the onset of spring has seen a sharp decline in the number of avian flu reports out of Europe we continue to see some lingering bird flu activity in western Russia. 
Last week Russian officials announced the discovery of avian flu in a small flock in a suburb of Moscow, while two weeks ago (see Russia: Rosselkhoznadzor Reports Bird Flu Outbreak In Rostov Region) we learned of a large avian flu  outbreak at the nation's largest turkey producer. 
Today, Russia's Federal Service for Veterinary and Phytosanitary Surveillance is reporting - somewhat cryptically - on the detection of `genetic material of bird flu virus' among poultry products shipped to Krasnodar from the Rostov Region. These appear to be linked to the poultry producer mentioned above.
The type of avian flu has not been specified in these reports, although HPAI H5 is a pretty good bet. The precise `product(s)'  - and whether any have reached store shelves - is equally vague.   
Even if bird flu positive products have been sold to the public, the risk of human infection is likely very low (particularly if the virus is H5N8).  If live birds, or eggs, have been sent to poultry facilities in Krasnodar, then there is a genuine risk of seeing this outbreak spread. 


This from Rosselkhoznadzor, followed by a report from TASS

About the discovery in the Krasnodar region of poultry products, containing the genetic material of the virus of avian influenza
May 2, 2017

© Central body
 
Studies of poultry products produced by "Evrodon" Rostov region received for implementation in different business entities of the Krasnodar Territory, held in GBU "Kropotkin edge veterinary laboratory." When held on April 28-29, 2017 laboratory tests had identified the genetic material of bird flu virus (type A), the results are confirmed, "ARRIAH" FGBU.

Infected with avian influenza virus of poultry products entered the Krasnodar region from the following suppliers: LLC "Trading House" Indolina "Oktyabrsky district of Rostov region, LLC" RHM - Taurus ", Rostov-on-Don, Rostov region," Company "Elitgrupp" Mr. Rostov-on-Don, Rostov region LLC "Krasnodar Grocery Home» Krasnodar, Krasnodar Krai.

Infected products identified April 27, 2017 on the territory of "Krasnodar Grocery Home» Sochi, dropped out of the enterprise without veterinary accompanying document in an unknown direction. Information on this fact sent to the law enforcement bodies to take measures to search for products.

This fact suggests that the avian influenza virus infected poultry products has been implemented outside of the Rostov region.

Rosselkhoznadzor addressed to the heads of executive authorities of the Russian Federation on the need for comprehensive measures to prevent the introduction of the agent highly pathogenic avian influenza in the territory of the Russian Federation, to strengthen control over the movement of the Russian Federation poultry and poultry products.

 And this from TASS.

Products "Evrodon" bird flu, got beyond the Rostov region

May 2, 13:01 UTC + 3

Information on this fact sent to the law enforcement bodies to take measures to search for products

MOSCOW, May 2. / TASS /. Part of the production of agricultural holding "Evrodon", the largest turkey producer in Russia infected with bird flu came to the realization of the limits of the Rostov region. It is reported by Rosselkhoznadzor .

"Infected products identified April 27, 2017 on the territory of LLC" Krasnodar grocery house "(Sochi), dropped out of the enterprise without veterinary accompanying documents to an unknown destination. This fact suggests that the avian influenza virus infected poultry products has been implemented beyond the Rostov region ", - said the agency.

Information on this fact sent to the law enforcement bodies to take measures to search for products.

Rosselkhoznadzor recalls that during April 28-29, laboratory studies have identified genetic material of bird flu virus (type A). Virus infected poultry products entered the Krasnodar region of the Trading House "Indolina" (Oktyabrsky District, Rostov region), "RHM - Taurus" (Rostov-on-Don), the company "Elitgrupp" (Rostov-on-Don) and "Krasnodar grocery home ".

The first outbreak of bird flu in the Rostov region were reported to "Evrodon" company in December 2016. Then it was necessary to destroy the 160 thous. Heads of birds. The company has estimated its losses in the amount of more than 1 billion rubles.

However, in late April 2017, Rosselkhoznadzor newly discovered bird flu at one of the "Evrodon". The company explained that management has taken measures to prevent the possible spread of the disease and euthanasia of birds held on the specified site (all were destroyed 42 thous. Heads). The cost of culling the company estimated at 16 million rubles.
 

Monday, May 01, 2017

Upcoming Webinar: The Strategic National Stockpile


#12,422


The Strategic National Stockpile is one of those low-profile agencies most Americans either know (or assume) exists, but know relatively little about.

Managed by the CDC and HHS, the SNS maintains, and can rapidly dispense during an emergency, supplies from its large inventory of vaccines, antibiotics, PPEs (Personal Protective Equipment), chemical antidotes, antitoxins and other items from undisclosed warehouse facilities around the nation.


Over the years, a few of the SNS related stories we've covered include:
Whether it be for a hurricane, a terrorist attack, a pandemic, or some other natural disaster, the SNS is our nation's ultimate `Doomsday Prepper'
Later this week the SNS - which just launched a new website - will hold a webinar - open to all public health officials and the general public - introducing, and familiarizing participants with our nations largest stockpile of emergency supplies.
Details on how to participate are at the link below. Attendance is limited, so register early.
Introduction to the Strategic National Stockpile on May 3, 2017 at 1:30 PM EST
Course

Webcast (live event) ID 1069826
Skill level: Introductory Course Number DSNSWEB22017

Description:  This learning webcast is designed to familiarize partners and stakeholders with the Centers for Disease Control and Prevention’s (CDC) Strategic National Stockpile, the nation’s largest supply of potentially life-saving pharmaceuticals and medical supplies for use in a public health emergency severe enough to cause local supplies to run out.
         (Continue . . . )


As impressive as the SNS is, it is a finite resource, and can not be expected to handle 100% of the nation's needs during a major crisis, like a pandemic, terrorist attack, or natural disaster. 
Its existence should not deter local governments, businesses, and individuals from preparing for their own needs during an emergency. 

For years the American Red Cross, FEMA, Ready.gov, and just about everyone else in emergency services has urged that individuals and families be prepared to deal for at least 72 hours after a major disaster. 
The operative words being, `at least’.  And with good reason. 
The logistics of delivering emergency assistance to millions of people - while hampered by bad weather, crippled communications, damaged infrastructure, or stressed supply chains - all within the first three days of a major disaster, are daunting, and in some cases may be impossible.

To become better prepared as an individual, family, business owner, or community to deal with all types of disasters, I would encourage you to visit the following preparedness sites.
FEMA http://www.fema.gov/index.shtm
READY.GOV http://www.ready.gov/
AMERICAN RED CROSS http://www.redcross.org/
A few of my (many) blogs on this subject include:

  • In An Emergency, Who Has Your Back?
  • When 72 Hours Isn’t Enough
  • When Evacuation Is The Better Part Of Valor

  • Because - as the folks running the SNS know - its really just a matter of time before the next disaster strikes.

    WHO Update & Summary On Liberia Outbreak Of Unknown Eitiology

    Liberia Cluster Map - Credit WHO


    #12,421


    The mystery surrounding the cluster of unexplained illnesses and deaths linked to a funeral  in Sinoe county, Liberia continues (see Friday's  WHO: Press Conference Notes On Cluster Of Unexplained Deaths In Liberia).

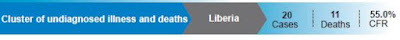
    While Ebola has been ruled out, and tests are ongoing, the lack of new cases is providing hope that this is due to some toxin or poison, rather than a communicable disease.  The current tally reads:


    The following report comes from the  WHO African Region weekly Outbreaks and other emergencies updates report for the week of April 22nd - 28th.
     
    This weekly report also covers a recent anthrax outbreak in Zimbabwe (14 cases, 1 death), along with the `grade 3 humanitarian crises in Nigeria and South Sudan, the grade 2 outbreaks of meningitis in Nigeria and necrotising cellulitis/fasciitis in Sao Tome and Principe, hepatitis E outbreak in Niger, and the food insecurity crisis in the Horn of Africa.'

    Cluster Of Undiagnosed Illnesses and Deaths - Liberia
             Event Description

    On 25 April 2017, the Liberia Ministry of Health notified WHO of a cluster of acute illness and sudden deaths due to an unknown aetiology in Sinoe county located in the southern region. The event, linked to a funeral function, started on 23 April 2017 when the index case, an 11 year old girl from Teah town, Greenville district developed an acute onset illness. She presented to FJ Grante hospital with diarrhoea, vomiting and mental confusion; and died within one hour of admission. The following day (24 April 2017), the second case-patient, a 51 year old woman from Teah town, Greenville developed sudden onset of vomiting, abdominal pain and confusion. She was admitted to FJ Grante hospital on 25 April 2017 and died the same day. On 25 April 2017 (the third day), a cluster of 13 case-patients from 5 communities in Greenville [Teah town - 6 cases, Congo town – 3 cases, Red hill - 2, Down town - 1, and Johnstone street - 1] developed similar acute onset illness. Seven out of the 13 case-patients died the same day on 25 April 2017.

    Between 23 and 27 April 2017, 20 case-patients presenting with similar illness were line-listed, 11 of those died, giving a case fatality rate of 55%. Over 80% (9/11) of the deaths occurred within the first 3 days (between 23 and 25 April 2017). Forty-two percent of the cases manifested with headache, 37% had vomiting, 27% had confusion, and 26% had abdominal pain and body weakness. Ninety five percent (19/20) of the cases came from Sinoe county. The first case outside Sinoe county (but linked to the funeral) occurred on 27 April 2017 in Montserrado county. Ten of the deaths took place in Sinoe and one in Montserrado. By 28 April 2017, 5 case-patients were admitted in F.J. Grant hospital in stable clinical condition. Fifty two close contacts have been listed and are being followed up on a daily basis for signs and symptoms of the illness.


    A total of 20 biological specimens were collected: 7 oral swabs, 7 whole blood, 3 urine, 2 cardiac fluid, and 1 rectal swab. Of these, the 7 oral swabs, 6 whole blood and 2 cardiac fluid tested negative for Ebola virus. One whole blood sample is still being tested for Ebola virus. Chemistry analysis on 3 urine specimens has not yielded any significant results. Further laboratory investigations for the pathogens including toxicological testing are ongoing. The first set of 11 samples have been shipped to Atlanta, United States. Another set of samples is being shipped to the WHO Reference Laboratory in South Africa.
    Over 95% of the line-listed cases participated in at least one aspect of the funeral rites of the religious leader who reportedly died of a known cause. The aspects of the funeral activities include burial, “repass” and “wake keeping”.

    Public health actions

    •The national and county epidemic preparedness and response committees have been reactivated to coordinate response to the event.
    •A multi-disciplinary national rapid response team has been deployed to Sinoe to conduct detailed outbreak investigation and support lower level outbreak response.
    •Active case search has been initiated in the affected and surrounding communities. Outbreak case definition has been developed to facilitate active case search among those who attended the funeral functions and others. Investigation and compilation of line list of all cases including systematic identification of contacts are ongoing.
    •Case management of patients currently admitted at the F.J. Grante Hospital is ongoing
    •County level advocacy meetings and community engagement have been conducted. The county health team has also embarked on mass public awareness.
    •Infection prevention and control interventions have been re-enforced including hand hygiene practices, water points testing and safe burials.
    Situation interpretation

    An alarming and a rapidly evolving situation unfolded in Liberia, understandably so, coming in the aftermath of the Ebola virus disease outbreak. While the dreaded Ebola virus disease has been ruled out in this event, there is still an urgent need to establish the ultimate aetiology of this cluster of acute illness and sudden deaths. The dramatic evolution of the event with very short course of illness and sudden death, and the clustering of the cases is indicative of a common source exposure to the pathogenic agent. All indications are pointing at the funeral functions of the religious leader. The likelihood of foods, drinks or water poisoning is high and the ongoing toxicology testing will be very critical to provide some answers. The overall risk of spread of the event is lowering with the sharp decline in the number of cases and deaths reported. No new cases and/or death have been reported since 28 April 2017.


    The Ministry of Health has requested WHO and CDC to expedite the process of toxicological testing outside the country. WHO is currently supporting the deployment of an experienced pathologist to do autopsy on one dead body that is preserved.


    The Government of Liberia and the Ministry of Health is being commended for the swift and effective response to this event, including the early detection and rapid deployment of response teams. The strong collaboration between WHO, CDC and the other partners in dealing with this event should set precedence for future response.