Monday, October 26, 2026

The UK's `Be Ready' Preparedness Campaign


#19,387

While Avian Flu Diary is primarily an infectious disease blog, individual and community preparedness (for all kinds of emergencies) is its secondary focus. In  its archives you'll find hundreds of preparedness articles (link).  

While calls for individual preparedness are common in the United States (see National Preparedness Month), in Europe is is far less often discussed. 

Eighteen months ago, however, the EU made headlines after calling for all households to prepare for a wide array of disasters (see excerpts below).

What type of crises is the EU preparing for? 

The EU is preparing for a broad spectrum of risks and threats, encompassing both natural and human-induced disasters. This includes:
  • Natural disasters: floods, wildfires, earthquakes, and extreme weather events exacerbated by climate change.
  • Human-induced disasters: industrial accidents, technological failures, and pandemics.
  • Hybrid threats: cyberattacks, disinformation campaigns and foreign information manipulation and interference (FIMI), and sabotage of critical infrastructure.
  • Geopolitical crises: armed conflicts, including the possibility of armed aggression against Member States.

       (SNIP)

Last December, we looked at the launch of  Denk Vooruit: The Netherlands National Citizen Preparedness Drive, on how to prepare for the first 72 hours of an emergency (e.g. extreme weather, cyberattacks, terrorist attack, even armed conflict, etc.).

Two months ago, in UK National Risk Register 2026 - Urges Citizen Preparedness, we looked at the UK government's sobering 223-page handbook for dealing with wide variety of  disaster scenarios. 


Late last week the UK quietly launched a new citizen preparedness campaign, which has gained a degree of internet notoriety over the weekend.  
Households encouraged to take small, simple steps to stay prepared in an emergency

Households are being encouraged to take a few simple steps to stay prepared if everyday services are temporarily disrupted, under updated advice published today.
Published:22 October 2026


Advice helps people feel better prepared for events such as severe weather, which can occasionally affect services like power, water, and the internet.

Campaign bolsters UK’s preparedness for emergencies, in line with European peers including France, Ireland and The Netherlands.
Simple steps include actions that are completely free, like signing up to the Priority Services Register, a service helping utility companies identify people most in need.

Households are being encouraged to take a few simple steps to stay prepared if everyday services are temporarily disrupted, under updated advice published today.

The advice is the first stage of a three-year campaign to help households across the UK feel better prepared for events such as severe weather, which can occasionally affect services including power, water, phones and the internet.

The campaign focuses on straightforward things people can do in advance, including signing up to the Priority Services Register - a service that helps gas, water, and electricity companies identify customers that may need extra support in an emergency - and keep a small supply of non-perishable food and bottled water at home.

With storms last winter and the wildfires this summer showing how severe weather events can cause disruption to our everyday lives and impact the services we rely on, from phone signal to water and the internet, launching the campaign brings the UK into line with European peers who all run similar campaigns already.

The government has worked with other countries to learn from their experience and best practice. For example, the advice to be prepared for three days of disruption that is at the heart of the UK campaign is also used by France, Ireland and The Netherlands.

The government has also worked closely with local resilience forums across the UK to root the advice in what works for local communities.

Dan Jarvis MP, Security Minister, said:
Those who can follow this advice should follow this advice. By taking simple steps to be ready for everyday emergencies like severe storms, people can reduce pressure on emergency services, helping them prioritise people who need more support in an emergency.

This is just the sort of community-focused campaign the UK needs to improve our resilience as a nation. It will bring us into line with European counterparts, where advice like this is a normal part of everyday life.
The ‘Be Ready’ campaign will build gradually over time. More than five hundred organisations across the UK, from charities to businesses, have already signed-up to share messaging and campaign assets within their networks and communities. Government channels like GOV.UK and social media accounts will also amplify content.

Over the coming weeks and months, social media and radio advertising will help reach audiences who may be particularly at-risk in everyday emergencies: families with young children and older people.

To ensure the updated advice is relevant and accessible to all, the ‘Be Ready’ campaign has been built in collaboration with charities and campaigners that work with groups that are often under-represented, including people with insecure housing and people who use foodbanks.

Many of the simple steps are quick and cost-free, like signing up to the Priority Services Register, and other steps are designed to be as low-cost as possible. The intention is that, if households that can take these steps do, emergency services will be able to prioritise those most in-need if an emergency were to happen.

The Government has published resilience advice for households since May 2024. While the ‘Be Ready’ campaign has seen the previous “Prepare” website updated with new messaging and branding, much of the advice has not changed and remains evergreen for households to follow.

Laura Scott, British Red Cross Director for UK Resilience, said:
We can’t control when emergencies happen, but we can all take some simple steps to be prepared, so that when they do, we are ready to help our friends, families and neighbours.

We know from our work across the UK that local people know their communities best and want to play a part when a crisis happens. Having clear and trusted advice for people, especially those who may be more at-risk, could help reduce the impact of crises and even save lives.

You can visit the UK's Be Ready Campaign webpage for more details.


As we discussed a month ago in #NPM26: Making Preparedness a Priority, I consider 72 hours the bare minimum level of preparedness, and would strongly recommend striving for 7 to 14 days. 

But it's a start. And once you achieve it, it can be added to over time. 

While no one can predict with any certainty what the next big regional or national emergency will be (in the UK, or anywhere else in the world),  a modicum of general preparedness can go a long way towards making a bad situation a little less dire. 

So . . . if a disaster struck your area today, and the power went out, stores closed their doors, and water stopped flowing from your kitchen tap for the next 7 to 14 days . . . do you already have:
  • A battery operated NWS Emergency Radio to find out what was going on, and to get vital instructions from emergency officials
  • A decent first-aid kit, so that you can treat injuries
  • Enough non-perishable food and water on hand to feed and hydrate your family (including pets) for the duration
  • A way to provide light when the grid is down.
  • A way to cook safely without electricity
  • A way to purify or filter water
  • A way to stay cool (fans) or warm when the power is out.
  • A small supply of cash to use in case credit/debit machines are not working
  • An emergency plan, including meeting places, emergency out-of-state contact numbers, a disaster buddy, and in case you must evacuate, a bug-out bag
  • Spare supply of essential prescription medicines that you or your family may need
  • A way to entertain yourself, or your kids, during a prolonged blackout
If your answer is `no’, then you're got some work to do. 

Sunday, October 25, 2026

Eurosurveillance: Fatal encephalitis caused by Shamonda virus Europe 1 (SHAV-EU1) in a patient with a severely weakened immune system, France, 2026


#19,386

In early August, we looked at a statement from the Swiss FSVO (Federal Office for Food Safety and Veterinary Affairs) on their Investigation into an Unidentified Bovine Disease which produced fevers, diarrhea, and substantial milk drop in dairy cows.

A few days later Germany's FLI (Friedrich Loeffler Institut) announced the results of their own investigation, which had discovered high levels of a novel orthobunyavirus of the Simbu serogroup present in affected cattle.

Orthobunyaviruses are a large and growing family of `arboviruses' - viruses carried and spread by biting insects and ticks (mosquitoes, ticks & midges) - that mostly infect animals, but are sometimes zoonotic.

The FLI's press release dated August 3rd stated:
Viruses of the Simbu serogroup are not generally considered to be zoonotic agents and, based on current knowledge, do not pose a significant risk of infection to humans. However, in the case of newly emerging and insufficiently characterised viruses in this group, their potential zoonotic risk should be investigated as a precautionary measure and closely monitored as the situation develops.

Last Thursday, the journal Eurosurveillance published the first account of a (fatal) human infection with this virus in a highly immunocompromised patient living in a rural region of France.

For now, this appears to be a rare occurrence, but investigations continue into the epidemiology of Shamonda-Europe 1 (SHAV-EU1) virus.

Due to its length  and technical detail, I've only posted some excerpts from the Eurosurveillance report. Follow the link to read the Rapid Communication in its entirety.  

I'll have a bit more after the break.  

Open Access
Volume 31, Issue 42, 22/Oct/2026

Fatal encephalitis caused by Shamonda virus Europe 1 (SHAV-EU1) in a patient with a severely weakened immune system, France, 2026  
Margot Bonnet1,* , Hélène Labussière-Wallet2,* , Pauline Dumez3,* , Lucie Jauffret4 , Lyderic Aubert5 , Aurélie Avondo-Ray5 , Carole Seurret3 , Perrine Devic3 , Sabrine Souci3 , Syria Laperche6 , Léa Saint Martin7 , Emilie Frobert7,8 , Alexandre Gaymard7,8 , Jennifer Giorgi7 , Quentin Semanas7 , Richard Chalvignac7 , Antoine Oblette7 , Audrey Lapendry7 , Bruno Pozzetto9 , Thomas Perpoint10 , Mikail Kelleci11 , Aurélie Sécula11 , Charlotte Foret-Lucas11 , Clement Javaux10 , Florence Morfin7,8 , Antonin Bal7,8 , Elise Brottet12 , Catarina Krug12 , Frederic Jourdain12 , David Meyronet13 , Florence Ader10,14 , Jean-Luc Guérin11,** , Laurence Josset7,8,** , Grégory Destras7,8,**

Clinical presentation

On 23 September 2026 (day (D)0), a patient in their sixties developed acute cortical blindness and confusion, with normal brain magnetic resonance imaging (MRI) and cerebrospinal fluid (CSF) examination. This patient had a history of T-cell prolymphocytic leukaemia diagnosed in November 2025. They underwent first-line treatment with alemtuzumab (Campath) from December 2025 to February 2026, followed by an allogeneic haematopoietic stem cell transplantation (HSCT) on D−28 from a human leukocyte antigen (HLA) matched related donor. The conditioning regimen consisted of thiotepa, fludarabine and busulfan and the graft vs host disease (GVHD) prophylaxis consisted of post-transplant cyclophosphamide and cyclosporine. The patient lived in a rural area in the French Rhône-Alpes region. They had been hospitalised in Lyon continuously since 18 August 2026, corresponding to D−36 (Figure 1).


(SNIP)


Discussion
 
Here, we report the first human case of SHAV-EU1 infection, an emerging Orthobunyavirus that spread over Europe in summer 2026 affecting predominantly cattle. The patient, who had a severely weakened immune system, died from multi-organ failure including neuro-invasive disease, with primary neurological symptoms appearing on 23 September.

Investigations into the viral course revealed that the virus was present in the patient's blood for several weeks. At this point, we cannot date the time of infection as the earliest sample investigated was already positive for the virus on 2 July. Given that the first detections in cattle were reported in early July and clinical signs were documented in dairy cattle as early as June 2026, the patient was probably infected between mid-June and 1 July 2026. Investigation of the patient’s clinical history revealed that they developed an episode of diarrhoea and anorexia on 19 June, similar to symptoms observed in adult cattle [2] and could correspond to the first symptoms of this infection. Investigations on earlier blood and available respiratory samples are ongoing to determine the first detection of the virus over the clinical course by RT-PCR as well as by genomic investigation.

Route of transmission also remains unknown at this point. Graft transmission has been ruled out due to the negative PCR test of the graft and the previous positive PCR of the blood sample. Three different transmission hypotheses are currently investigated. As observed in animals, the most likely is the vector-borne transmission, presumably Culicoides spp. biting midges near the patient's home located in a rural area where animal transmission of SHAV-EU1 was officially documented in early July 2026, although transmission was likely already occurring in June 2026. The potential involvement of alternative arthropod vectors should also be explored. The two other routes (transfusion and food-borne) are less likely, given the sequence of events, and are not supported by any evidence at this point although investigations are ongoing to rule them out. Transfusion-related transmission would require an immunocompetent donor with asymptomatic viraemia in June, while viraemia is reported very transient in animals. Transmission by raw milk or raw cheese appears unlikely, as the presence of the virus in milk has not yet been reported and there is currently no evidence of direct contact-mediated transmission between animals.

(SNIP)

Conclusion

We present the first case of human infection by the Shamonda-Europe virus, specifically the clade EU1, which emerged in European animals in June 2026. However, given the patient’s significantly weakened immune system, this finding alone cannot currently be interpreted as a serious risk for the general immunocompetent population. 

The primary hypothesis of transmission remains Culicoides biting midges and although direct human-to-human transmission appears unlikely, transmission through blood transfusion or organ transplantation remains a potential concern. Further investigations are warranted to better characterise transmission routes, particularly potential vector-borne transmission. This case calls for an enhanced surveillance of Shamonda Europe virus in both human and animal settings in Europe.

        (Continue . . . )

Fifteen years and more than 15,000 blog posts ago, I wrote a piece called The Third Epidemiological Transition, based on the works of the now late (May 22, 1936 - May 15, 2014) anthropologist and researcher George Armelagos of Emory University.

The gist of his theory - which he first published in the mid-1990s - was that since the mid-1970s the world had entered into an age of newly emerging infectious diseases, re-emerging diseases and a rise in antimicrobial resistant pathogens.

While most of these threats will never rise to pandemic proportions, their impact on our lives and our economies can still be significant. Our current battles with measles in North America  and dengue fever in Florida, are just two of many examples. 

While the Shamonda-Europe virus seems unlikely to pose a significant public health threat, one can never truly predict what an emerging disease will do.  Viruses can evolve, environmental conditions can change, and suddenly a minor threat can become more formidable. 

Which is why there is value in our tracking these outbreaks, even when they seem mostly of academic interest at the time. 

Saturday, October 24, 2026

Texas & Washington Report More H5N1 in Dairy Cows & FluView Wk 41 Update


#19,385

Just over 2 weeks ago (Oct 8th) USDA/APHIS announced the first detection of H5N1 in dairy cattle in Washington State, which was followed a week later by the first (reportedly mild) human H5N1 infection reported in the U.S. in 2026 (see Washington State Confirms Human Avian Flu Infection).

Since then, we've seen the number of infected dairy herds in Washington state rise to 3, then 8 - and as of yesterday - 9. 

Meanwhile, the USDA reports that Texas has detected four infected herds in the past 30 days, and Kansas has reported one.  While details on how the HPAI virus was introduced into Washington's dairy herds, how it is spreading, and the genotype have been scant, overnight GISAID announced the Washington human case was B3.13.

Recently, genetic sequence data was released on GISAID from a case of captive American mink and cases of dairy cows from Idaho and Utah from the B3.13 lineage (ggFlu genotype E.2). Some of these sequences presented mutations associated with antigenic drift/escape and mild drug resistance.

On 12 October 2026, the first case of a human H5N1 infection this year was detected in Washington State. The sequence (EPI_ISL_205571770) clusters with recent samples from Idaho and Utah, carrying the same mutation in the NA segment.

Yesterday, the CDC's weekly FluView report noted:

Novel Influenza A Virus Infections

One confirmed human infection with avian influenza A(H5N1) virus was reported to CDC this week. To date, human-to-human transmission of influenza A(H5) virus has not been identified in the United States.

The case was reported by the Washington State Department of Health and occurred in a worker aged ≥18 years at a commercial dairy cattle farm where highly pathogenic avian influenza (HPAI) A(H5N1) virus has been detected in cows. This individual developed eye irritation and upper respiratory symptoms, which they reported to the local health department. Specimens were collected from the individual and tested at the state public health laboratory using the CDC influenza A(H5) assay during the week ending October 17, 2026 (Week 41). Influenza A(H5) virus was confirmed by the state public health laboratory. Additional testing conducted by CDC determined this was an influenza A(H5N1) virus. This is the first influenza A(H5) case associated with a dairy worker in Washington.

While influenza activity in the United States remains low, the FluView report indicates it is rising.  Since seasonal influenza continues to evolve, this year's Northern Hemisphere vaccine contains 3 new components (H1N1, H3N2, Influenza B).

A little over a month ago, in Preprint: Near real-time data on the human neutralizing antibody landscape to influenza virus in summer of 2026 shows antigenic advance of H3N2 subclade K region D mutants and H1N1 D.3.1.1 Sa mutants, we looked at some of this ongoing evolution. 

Among their findings, the authors identified 72 serum samples in which an H1N1 D.3.1.1 virus carrying G155E was more than twofold less effectively neutralized than a comparable virus without that mutation. Those samples tended to come from teenagers and young adults (roughly 15–25 years old).

While it isn't clear how much - if any - impact this will have on this year's flu vaccine effectiveness, this week's FluView carries the following caveat:

  • Since Week 21 (the week ending May 30, 2026), 81.5% of the influenza A viruses reported have been A(H1N1)pdm09 and among these, the majority have been D.3.1.1 HA subclade.
  • The A(H1N1) viruses detected this season are still A(H1N1)pdm09 viruses, which emerged in 2009 and have caused seasonal epidemics globally since then. Influenza viruses are constantly changing, usually requiring updates to influenza vaccine viruses each season. Historically, influenza A(H1N1)pdm09 viruses have changed less often than A(H3N2) viruses. Recently circulating influenza A(H1N1)pdm09 viruses (which are in an HA subclade called "D.3.1.1") are dividing into different groups showing different genetic changes. It is too early to know what viruses may predominate or to say whether there might be implications on flu vaccine effectiveness this season.
In addition to these antigenic changes, we are also following concurrent reports of creeping antiviral resistance in H1N1 (see Eurosurveillance: Emergence and spread of NA-I223V and NA-S247N double-mutant A(H1N1)pdm09 influenza viruses with reduced oseltamivir susceptibility in the Netherlands and beyond, 2023 to 2026).

Last week I reported that the CDC had announced 8 H1N1 viruses tested over the summer showed resistance markers.  This week's FluView leaves that number unchanged.  

Our last stop is the USDA's poultry HPAI dashboard, which shows an October  uptick in both backyard and commercial outbreaks.  Although commercial operations see the biggest losses in birds, backyard flocks are more often affected. 


While most commercial poultry producers have a good deal of experience in dealing with outbreaks, surveys indicate that backyard producers are generally less well aware of the signs of avian flu, and may be less inclined to wear PPE.  

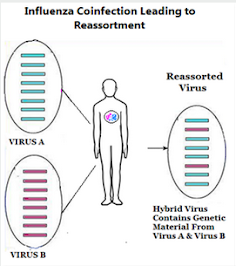
Attempts to convince high-risk poultry and dairy workers to get the seasonal flu shot - which is hoped will reduce the risks of coinfection and potential reassortment - continue to yield disappointing results.  

Antigenic `Shift' or Reassortment 

While the severity and impact of this year's flu season remains unknown, we are seeing mounting pressures from both seasonal and novel flu which could potentially complicate matters.

All reasons why I've updated my Flu, COVID, and Pneumovax vaccines, and will happily don an N95 mask in crowded indoor venues. 

None of which guarantees I'll come away unscathed this winter, but it certainly increases my chances.  And at my age, I'll take any advantage I can get. 

Friday, October 23, 2026

Virological (Referral): Preliminary report on H5N1 highly pathogenic avian influenza in Utah mink, August 2026

#19,384

Two months ago, in That Touch of Mink Flu (H5N1 in Utah Edition), we looked at a cryptic announcement of an outbreak of HPAI H5N1 at a mink farm in Utah.  Mink - along with other members of the Mustelidae family of carnivorous mammals (e.g. otters, badgers, weasels, martens, and ferrets) are highly susceptible to both COVID and flu infection.

Over the past 20 years we've looked at a number of concerning spillovers, including:
  • 2009's That Touch Of Mink Flu, where at least 11 mink farms in the Holstebro municipality of Denmark were reported to be infected with a variant of the human H3N2 virus.

Roughly a month later, in H5N1 in Utah Mink (Updated), we looked at local reporting on the incident, but details on the actual outbreak remained scant. 

Yesterday, we saw our first detailed account - posted on the Virological.org discussion forum - penned by researchers from the NIH, the Pirbright Institute, Imperial College, London, and Sorbonne Université. 

Since this is not explicitly listed as available under a creative commons license (there is very old CC 3.0 notice under terms of use), I'm going to only briefly summarize the findings, and urge my readers to follow the link and read it in its entirety. 

Briefly, the authors report that: 
  • Based on 10 samples taken on Aug 7th - the H5N1 virus detected was the `Bovine' B3.13 genotype. It carried the pre-existing cattle PB2-M631L adaptation, along with NA mutations K432E and N434S.
  • Of note, all ten mink viruses carry PB1-K388R, which was seen in the 2022 Spanish mink outbreak, which is rarely seen in birds, and absent in cattle. 
  • The mink viruses most closely resemble the 2026 cattle clade (Idaho, Texas, Utah), with the closest match being Texas cattle viruses sampled May 28, 2026.
  • The most recent common ancestor is estimated to date back to about July 4 (95% HPD June 21–July 15), and suggests a single introduction followed by weeks of undetected spread.
  • While wild birds were considered the most likely source of mink outbreaks in Spain and Finland, they report `. . . the transmission route between Texas cattle to Utah mink is considerably less clear.'
  • Since only the Aug 7th sequences have been released, we don't know if additional mutations may have occurred.  As of late September the outbreak was still reportedly ongoing, and no culling had been undertaken. 

The link to the full report follows. I'll have a brief postscript after the break. 

Preliminary report on H5N1 highly pathogenic avian influenza in Utah mink, August 2026

Influenza virus H5N1-global

Oct 22
post by Martha_NIH 14 hours ago


Martha_NIH
 
Alvin Crespo-Bellido1, Jennifer L. Havens1, Thomas P. Peacock2,3, Florence Débarre4, Martha I. Nelson1

1 Division of Intramural Research, National Library of Medicine, National Institutes of Health, Bethesda, MD USA
2 The Pirbright Institute, Woking, UK
3Department of Infectious Disease, Imperial College London, UK
4 Institut d’Écologie et des Sciences de l’Environnement, CNRS, Sorbonne Université, UPEC, IRD, INRAE, Paris, France


During the height of Finland's fur farm epizootic in 2023, we looked at an opinion piece by one of today's authors - Thomas P. Peacock (along with Professor Wendy Barclay) - on why fur farms - and mink farms in particular - are high-risk venues for novel flu.

Six week ago, in  The Lancet Regional Health Europe (Comment): If the EU is serious about One Health, it must ban fur farming, we looked at a similar call to action. 

While some EU countries have taken steps to phase out or ban fur farming, the industry continues in many parts of the world, including China, Russia, the United States, Canada and parts of the EU.

Whether we can summon the political will to do something about these risks before a genuine public health threat emerges, remains to be seen.  

Thursday, October 22, 2026

FAO: Call to Strengthen Prevention, Surveillance, and Preparedness against HPAI in Latin America and the Caribbean


#19,383

Although HPAI H5 has reached nearly every corner of the world, reporting from many regions remains spotty at best. Sometimes this data is deliberately withheld for political or economic reasons, but often it is due to a lack of resources, or difficulties conducting surveillance in remote or uninhabited regions. 

The FAO's map of 2025-2026 Global AIV activity illustrates these gaps:

Large swaths of Asia, Africa, South and Central America, and Northern Canada are essentially a blank slate. Yet we know, based on bird migratory patterns (flyways), that HPAI incursions almost certainly are occurring. 

Major Global Migratory Flyways – Credit FAO

Last week the FAO issued an alert to Latin American and Caribbean nations advising them to strengthen their surveillance for - and preparedness against - HPAI as the coming months are likely to see an increased risk for outbreaks. 

Due to its length, I've only posted some excerpts. Follow the link to read the document in its entirety.  I'll have a brief postscript after the break.


CALL TO STRENGTHEN PREVENTION, SURVEILLANCE AND PREPAREDNESS MEASURES AGAINST HIGH PATHOGENICITY AVIAN INFLUENZA IN LATIN AMERICA AND THE CARIBBEAN
16 October 2026


Given the continued circulation of high pathogenicity avian influenza (HPAI) viruses in the Americas and the proximity of a period of increased risk associated with the seasonal movements of migratory wild birds from the northern hemisphere to Latin America and the Caribbean, FAO calls on official veterinary services, public health authorities, poultry producers and other stakeholders involved in animal health to strengthen prevention, surveillance, early detection and response preparedness measures against this disease.

HPAI continues to pose a health threat to poultry, wildlife and potentially other animal species and people. Avian influenza A(H5) viruses have continued to circulate across the continent in 2026. More than 10 countries in the Americas have reported over 1 000 outbreaks and cases in domestic, wild and mammalian animals, according to data from the World Organisation for Animal Health (WOAH) and the countries.

Experience over the past few years shows that wild birds, particularly migratory waterbirds, can play an important role in the geographical spread of avian influenza viruses. The migration and concentration of birds from different geographical areas provide opportunities for virus circulation and can increase the risk of introduction of the virus into domestic bird populations. According to official WOAH data and analysis of FAO EMPRES-i+ data over the past few years, HPAI outbreaks tend to increase from October and reach their highest levels during the following months.

For this reason, the coming period requires increased vigilance and preparedness, especially in countries, territories and areas along migratory routes, in wetlands, lagoons, coastal areas or other places where wild birds congregate, and in areas where poultry farms are located close to these environments.

Avian influenza is a highly contagious viral disease that mainly affects domestic and wild birds. However, during the current epidemiological situation, infections have also been identified in various species of terrestrial and marine mammals.

In addition, certain avian influenza viruses have zoonotic potential and can occasionally infect humans, mainly in situations of close contact and without adequate protection with infected animals or contaminated environments. Although the risk to the general population is still considered low, surveillance should be maintained, especially among people with occupational or frequent exposure to potentially infected animals (Pan American Health Organization, (Pan American Health Organization, PAHO).

Based on the FAO-WOAH Global strategy for the prevention and control of high pathogenicity avian influenza (2024-2033) – Achieving sustainable, resilient poultry production systems, the FAO Regional Office for Latin America and the Caribbean provides specific recommendations for veterinary services and poultry producers.


While it is impossible to achieve anything approaching 100% surveillance, the more information we can gather and share, the less likely we are to be blindsided by an abrupt evolutionary change in the virus. 

But whether that is enough of an incentive to see real change in the amount and quality of global surveillance and reporting on HPAI remains to be seen.   

CDC COCA Call Today: What Clinicians Need to Know about Dengue in the United States


#19,382

Later today (Thursday, Oct 22nd) the CDC will hold a COCA Call for clinicians and other healthcare professionals on this year's record breaking spread of Dengue in Florida (see chart above).

Carried and spread by mosquitoes, Dengue fever first returned to Florida in 2009 after an absence of nearly 70 years  (see 2010 MMWR report Locally Acquired Dengue --- Key West, Florida, 2009--2010). 

The virus was likely imported by someone with recent travel to a dengue endemic region who served as a blood meal for a local mosquito, which then began spreading the virus to others. 

Initially, more than 2 dozen Dengue patients were identified in and around Key West in the fall of 2009, although a year later, the CDC would report far more people were exposed (see CDC Press Release Report Suggests Nearly 5 Percent Exposed to Dengue Virus in Key West).

This year, the Florida Department of Health has recorded nearly 300 imported cases (see chart below), with the vast majority linked to Cuba. 


This year's locally acquired outbreak is the largest reported by Florida since the 1940s. While this may seem primarily a `Florida problem' -  this is a tourist state - and doctors anywhere in the country (and internationally) could see Dengue cases arising from this outbreak.  
Accordingly, the CDC will hold a COCA (Clinician Outreach & Communication Activity) call this afternoon. While these presentations are often technical and are of greatest interest to clinicians and healthcare providers, they are usually archived within a few days, and made available to the general public.
Details on today's presentation follow:

What Clinicians Need to Know about Dengue in the United States

For Health Care Providers
Oct. 22, 2026, visit link for details.

At a glance

During this COCA Call, presenters will discuss current dengue epidemiology in the United States and review dengue clinical features, current diagnostic testing recommendations, and clinical management guidelines.

Overview

Dengue virus is endemic in several U.S. territories and freely associated states and has caused increasing numbers of travel-associated and locally acquired dengue cases in U.S. states in recent years. No preventative medicines or specific antiviral treatments are available for dengue. Severe dengue is a medical emergency—recognition of warning signs and appropriate clinical management are critical for reducing severe outcomes. During this COCA Call, presenters will discuss current dengue epidemiology in the United States and review dengue clinical features, current diagnostic testing recommendations, and clinical management guidelines.

Webinar

Call Details

Date & Time: Thursday, October 22, 2026 - 2:00 – 3:00 PM ET

A few minutes before the webinar begins, please click this link to join.


Presenters

Laura Adams, DVM, MPH, DACVPM
Epidemiologist
Dengue Branch, Division of Vector-Borne Diseases
National Center for Emerging and Zoonotic Infectious Diseases
Centers for Disease Control and Prevention

Liliana Sánchez-González, MD, MPH, CTropMed
Medical Epidemiologist
Dengue Branch, Division of Vector-Borne Diseases
National Center for Emerging and Zoonotic Infectious Diseases
Centers for Disease Control and Prevention

Call Objectives

COCA Call Objectives


At the conclusion of the session, the participant will be able to accomplish the following:
  • Cite background information on the topic covered during the presentation.
  • Identify CDC's role in the topic covered during the presentation.
  • Describe the topic's implications for clinicians.
  • Identify concerns and issues related to preparedness for and response to urgent public health threats.
  • Identify how an interprofessional team of healthcare providers can work with patients to promote disease prevention.
Activity-specific Objectives

At the conclusion of this session, the participant will be able to accomplish the following:
  • Summarize dengue epidemiology and transmission in the United States.
  • List the clinical features of dengue.
  • Explain dengue diagnostic testing for patients with suspected dengue.
  • Describe appropriate treatment for dengue patients according to severity classification.