Saturday, October 24, 2026

Texas & Washington Report More H5N1 in Dairy Cows & FluView Wk 41 Update


#19,385

Just over 2 weeks ago (Oct 8th) USDA/APHIS announced the first detection of H5N1 in dairy cattle in Washington State, which was followed a week later by the first (reportedly mild) human H5N1 infection reported in the U.S. in 2026 (see Washington State Confirms Human Avian Flu Infection).

Since then, we've seen the number of infected dairy herds in Washington state rise to 3, then 8 - and as of yesterday - 9. 

Meanwhile, the USDA reports that Texas has detected four infected herds in the past 30 days, and Kansas has reported one.  While details on how the HPAI virus was introduced into Washington's dairy herds, how it is spreading, and the genotype have been scant, overnight GISAID announced the Washington human case was B3.13.

Recently, genetic sequence data was released on GISAID from a case of captive American mink and cases of dairy cows from Idaho and Utah from the B3.13 lineage (ggFlu genotype E.2). Some of these sequences presented mutations associated with antigenic drift/escape and mild drug resistance.

On 12 October 2026, the first case of a human H5N1 infection this year was detected in Washington State. The sequence (EPI_ISL_205571770) clusters with recent samples from Idaho and Utah, carrying the same mutation in the NA segment.

Yesterday, the CDC's weekly FluView report noted:

Novel Influenza A Virus Infections

One confirmed human infection with avian influenza A(H5N1) virus was reported to CDC this week. To date, human-to-human transmission of influenza A(H5) virus has not been identified in the United States.

The case was reported by the Washington State Department of Health and occurred in a worker aged ≥18 years at a commercial dairy cattle farm where highly pathogenic avian influenza (HPAI) A(H5N1) virus has been detected in cows. This individual developed eye irritation and upper respiratory symptoms, which they reported to the local health department. Specimens were collected from the individual and tested at the state public health laboratory using the CDC influenza A(H5) assay during the week ending October 17, 2026 (Week 41). Influenza A(H5) virus was confirmed by the state public health laboratory. Additional testing conducted by CDC determined this was an influenza A(H5N1) virus. This is the first influenza A(H5) case associated with a dairy worker in Washington.

While influenza activity in the United States remains low, the FluView report indicates it is rising.  Since seasonal influenza continues to evolve, this year's Northern Hemisphere vaccine contains 3 new components (H1N1, H3N2, Influenza B).

A little over a month ago, in Preprint: Near real-time data on the human neutralizing antibody landscape to influenza virus in summer of 2026 shows antigenic advance of H3N2 subclade K region D mutants and H1N1 D.3.1.1 Sa mutants, we looked at some of this ongoing evolution. 

Among their findings, the authors identified 72 serum samples in which an H1N1 D.3.1.1 virus carrying G155E was more than twofold less effectively neutralized than a comparable virus without that mutation. Those samples tended to come from teenagers and young adults (roughly 15–25 years old).

While it isn't clear how much - if any - impact this will have on this year's flu vaccine effectiveness, this week's FluView carries the following caveat:

  • Since Week 21 (the week ending May 30, 2026), 81.5% of the influenza A viruses reported have been A(H1N1)pdm09 and among these, the majority have been D.3.1.1 HA subclade.
  • The A(H1N1) viruses detected this season are still A(H1N1)pdm09 viruses, which emerged in 2009 and have caused seasonal epidemics globally since then. Influenza viruses are constantly changing, usually requiring updates to influenza vaccine viruses each season. Historically, influenza A(H1N1)pdm09 viruses have changed less often than A(H3N2) viruses. Recently circulating influenza A(H1N1)pdm09 viruses (which are in an HA subclade called "D.3.1.1") are dividing into different groups showing different genetic changes. It is too early to know what viruses may predominate or to say whether there might be implications on flu vaccine effectiveness this season.
In addition to these antigenic changes, we are also following concurrent reports of creeping antiviral resistance in H1N1 (see Eurosurveillance: Emergence and spread of NA-I223V and NA-S247N double-mutant A(H1N1)pdm09 influenza viruses with reduced oseltamivir susceptibility in the Netherlands and beyond, 2023 to 2026).

Last week I reported that the CDC had announced 8 H1N1 viruses tested over the summer showed resistance markers.  This week's FluView leaves that number unchanged.  

Our last stop is the USDA's poultry HPAI dashboard, which shows an October  uptick in both backyard and commercial outbreaks.  Although commercial operations see the biggest losses in birds, backyard flocks are more often affected. 


While most commercial poultry producers have a good deal of experience in dealing with outbreaks, surveys indicate that backyard producers are generally less well aware of the signs of avian flu, and may be less inclined to wear PPE.  

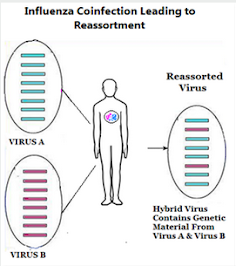
Attempts to convince high-risk poultry and dairy workers to get the seasonal flu shot - which is hoped will reduce the risks of coinfection and potential reassortment - continue to yield disappointing results.  

Antigenic `Shift' or Reassortment 

While the severity and impact of this year's flu season remains unknown, we are seeing mounting pressures from both seasonal and novel flu which could potentially complicate matters.

All reasons why I've updated my Flu, COVID, and Pneumovax vaccines, and will happily don an N95 mask in crowded indoor venues. 

None of which guarantees I'll come away unscathed this winter, but it certainly increases my chances.  And at my age, I'll take any advantage I can get. 

Friday, October 23, 2026

Virological (Referral): Preliminary report on H5N1 highly pathogenic avian influenza in Utah mink, August 2026

#19,384

Two months ago, in That Touch of Mink Flu (H5N1 in Utah Edition), we looked at a cryptic announcement of an outbreak of HPAI H5N1 at a mink farm in Utah.  Mink - along with other members of the Mustelidae family of carnivorous mammals (e.g. otters, badgers, weasels, martens, and ferrets) are highly susceptible to both COVID and flu infection.

Over the past 20 years we've looked at a number of concerning spillovers, including:
  • 2009's That Touch Of Mink Flu, where at least 11 mink farms in the Holstebro municipality of Denmark were reported to be infected with a variant of the human H3N2 virus.

Roughly a month later, in H5N1 in Utah Mink (Updated), we looked at local reporting on the incident, but details on the actual outbreak remained scant. 

Yesterday, we saw our first detailed account - posted on the Virological.org discussion forum - penned by researchers from the NIH, the Pirbright Institute, Imperial College, London, and Sorbonne Université. 

Since this is not explicitly listed as available under a creative commons license (there is very old CC 3.0 notice under terms of use), I'm going to only briefly summarize the findings, and urge my readers to follow the link and read it in its entirety. 

Briefly, the authors report that: 
  • Based on 10 samples taken on Aug 7th - the H5N1 virus detected was the `Bovine' B3.13 genotype. It carried the pre-existing cattle PB2-M631L adaptation, along with NA mutations K432E and N434S.
  • Of note, all ten mink viruses carry PB1-K388R, which was seen in the 2022 Spanish mink outbreak, which is rarely seen in birds, and absent in cattle. 
  • The mink viruses most closely resemble the 2026 cattle clade (Idaho, Texas, Utah), with the closest match being Texas cattle viruses sampled May 28, 2026.
  • The most recent common ancestor is estimated to date back to about July 4 (95% HPD June 21–July 15), and suggests a single introduction followed by weeks of undetected spread.
  • While wild birds were considered the most likely source of mink outbreaks in Spain and Finland, they report `. . . the transmission route between Texas cattle to Utah mink is considerably less clear.'
  • Since only the Aug 7th sequences have been released, we don't know if additional mutations may have occurred.  As of late September the outbreak was still reportedly ongoing, and no culling had been undertaken. 

The link to the full report follows. I'll have a brief postscript after the break. 

Preliminary report on H5N1 highly pathogenic avian influenza in Utah mink, August 2026

Influenza virus H5N1-global

Oct 22
post by Martha_NIH 14 hours ago


Martha_NIH
 
Alvin Crespo-Bellido1, Jennifer L. Havens1, Thomas P. Peacock2,3, Florence Débarre4, Martha I. Nelson1

1 Division of Intramural Research, National Library of Medicine, National Institutes of Health, Bethesda, MD USA
2 The Pirbright Institute, Woking, UK
3Department of Infectious Disease, Imperial College London, UK
4 Institut d’Écologie et des Sciences de l’Environnement, CNRS, Sorbonne Université, UPEC, IRD, INRAE, Paris, France


During the height of Finland's fur farm epizootic in 2023, we looked at an opinion piece by one of today's authors - Thomas P. Peacock (along with Professor Wendy Barclay) - on why fur farms - and mink farms in particular - are high-risk venues for novel flu.

Six week ago, in  The Lancet Regional Health Europe (Comment): If the EU is serious about One Health, it must ban fur farming, we looked at a similar call to action. 

While some EU countries have taken steps to phase out or ban fur farming, the industry continues in many parts of the world, including China, Russia, the United States, Canada and parts of the EU.

Whether we can summon the political will to do something about these risks before a genuine public health threat emerges, remains to be seen.  

Thursday, October 22, 2026

FAO: Call to Strengthen Prevention, Surveillance, and Preparedness against HPAI in Latin America and the Caribbean


#19,383

Although HPAI H5 has reached nearly every corner of the world, reporting from many regions remains spotty at best. Sometimes this data is deliberately withheld for political or economic reasons, but often it is due to a lack of resources, or difficulties conducting surveillance in remote or uninhabited regions. 

The FAO's map of 2025-2026 Global AIV activity illustrates these gaps:

Large swaths of Asia, Africa, South and Central America, and Northern Canada are essentially a blank slate. Yet we know, based on bird migratory patterns (flyways), that HPAI incursions almost certainly are occurring. 

Major Global Migratory Flyways – Credit FAO

Last week the FAO issued an alert to Latin American and Caribbean nations advising them to strengthen their surveillance for - and preparedness against - HPAI as the coming months are likely to see an increased risk for outbreaks. 

Due to its length, I've only posted some excerpts. Follow the link to read the document in its entirety.  I'll have a brief postscript after the break.


CALL TO STRENGTHEN PREVENTION, SURVEILLANCE AND PREPAREDNESS MEASURES AGAINST HIGH PATHOGENICITY AVIAN INFLUENZA IN LATIN AMERICA AND THE CARIBBEAN
16 October 2026


Given the continued circulation of high pathogenicity avian influenza (HPAI) viruses in the Americas and the proximity of a period of increased risk associated with the seasonal movements of migratory wild birds from the northern hemisphere to Latin America and the Caribbean, FAO calls on official veterinary services, public health authorities, poultry producers and other stakeholders involved in animal health to strengthen prevention, surveillance, early detection and response preparedness measures against this disease.

HPAI continues to pose a health threat to poultry, wildlife and potentially other animal species and people. Avian influenza A(H5) viruses have continued to circulate across the continent in 2026. More than 10 countries in the Americas have reported over 1 000 outbreaks and cases in domestic, wild and mammalian animals, according to data from the World Organisation for Animal Health (WOAH) and the countries.

Experience over the past few years shows that wild birds, particularly migratory waterbirds, can play an important role in the geographical spread of avian influenza viruses. The migration and concentration of birds from different geographical areas provide opportunities for virus circulation and can increase the risk of introduction of the virus into domestic bird populations. According to official WOAH data and analysis of FAO EMPRES-i+ data over the past few years, HPAI outbreaks tend to increase from October and reach their highest levels during the following months.

For this reason, the coming period requires increased vigilance and preparedness, especially in countries, territories and areas along migratory routes, in wetlands, lagoons, coastal areas or other places where wild birds congregate, and in areas where poultry farms are located close to these environments.

Avian influenza is a highly contagious viral disease that mainly affects domestic and wild birds. However, during the current epidemiological situation, infections have also been identified in various species of terrestrial and marine mammals.

In addition, certain avian influenza viruses have zoonotic potential and can occasionally infect humans, mainly in situations of close contact and without adequate protection with infected animals or contaminated environments. Although the risk to the general population is still considered low, surveillance should be maintained, especially among people with occupational or frequent exposure to potentially infected animals (Pan American Health Organization, (Pan American Health Organization, PAHO).

Based on the FAO-WOAH Global strategy for the prevention and control of high pathogenicity avian influenza (2024-2033) – Achieving sustainable, resilient poultry production systems, the FAO Regional Office for Latin America and the Caribbean provides specific recommendations for veterinary services and poultry producers.


While it is impossible to achieve anything approaching 100% surveillance, the more information we can gather and share, the less likely we are to be blindsided by an abrupt evolutionary change in the virus. 

But whether that is enough of an incentive to see real change in the amount and quality of global surveillance and reporting on HPAI remains to be seen.   

CDC COCA Call Today: What Clinicians Need to Know about Dengue in the United States


#19,382

Later today (Thursday, Oct 22nd) the CDC will hold a COCA Call for clinicians and other healthcare professionals on this year's record breaking spread of Dengue in Florida (see chart above).

Carried and spread by mosquitoes, Dengue fever first returned to Florida in 2009 after an absence of nearly 70 years  (see 2010 MMWR report Locally Acquired Dengue --- Key West, Florida, 2009--2010). 

The virus was likely imported by someone with recent travel to a dengue endemic region who served as a blood meal for a local mosquito, which then began spreading the virus to others. 

Initially, more than 2 dozen Dengue patients were identified in and around Key West in the fall of 2009, although a year later, the CDC would report far more people were exposed (see CDC Press Release Report Suggests Nearly 5 Percent Exposed to Dengue Virus in Key West).

This year, the Florida Department of Health has recorded nearly 300 imported cases (see chart below), with the vast majority linked to Cuba. 


This year's locally acquired outbreak is the largest reported by Florida since the 1940s. While this may seem primarily a `Florida problem' -  this is a tourist state - and doctors anywhere in the country (and internationally) could see Dengue cases arising from this outbreak.  
Accordingly, the CDC will hold a COCA (Clinician Outreach & Communication Activity) call this afternoon. While these presentations are often technical and are of greatest interest to clinicians and healthcare providers, they are usually archived within a few days, and made available to the general public.
Details on today's presentation follow:

What Clinicians Need to Know about Dengue in the United States

For Health Care Providers
Oct. 22, 2026, visit link for details.

At a glance

During this COCA Call, presenters will discuss current dengue epidemiology in the United States and review dengue clinical features, current diagnostic testing recommendations, and clinical management guidelines.

Overview

Dengue virus is endemic in several U.S. territories and freely associated states and has caused increasing numbers of travel-associated and locally acquired dengue cases in U.S. states in recent years. No preventative medicines or specific antiviral treatments are available for dengue. Severe dengue is a medical emergency—recognition of warning signs and appropriate clinical management are critical for reducing severe outcomes. During this COCA Call, presenters will discuss current dengue epidemiology in the United States and review dengue clinical features, current diagnostic testing recommendations, and clinical management guidelines.

Webinar

Call Details

Date & Time: Thursday, October 22, 2026 - 2:00 – 3:00 PM ET

A few minutes before the webinar begins, please click this link to join.


Presenters

Laura Adams, DVM, MPH, DACVPM
Epidemiologist
Dengue Branch, Division of Vector-Borne Diseases
National Center for Emerging and Zoonotic Infectious Diseases
Centers for Disease Control and Prevention

Liliana Sánchez-González, MD, MPH, CTropMed
Medical Epidemiologist
Dengue Branch, Division of Vector-Borne Diseases
National Center for Emerging and Zoonotic Infectious Diseases
Centers for Disease Control and Prevention

Call Objectives

COCA Call Objectives


At the conclusion of the session, the participant will be able to accomplish the following:
  • Cite background information on the topic covered during the presentation.
  • Identify CDC's role in the topic covered during the presentation.
  • Describe the topic's implications for clinicians.
  • Identify concerns and issues related to preparedness for and response to urgent public health threats.
  • Identify how an interprofessional team of healthcare providers can work with patients to promote disease prevention.
Activity-specific Objectives

At the conclusion of this session, the participant will be able to accomplish the following:
  • Summarize dengue epidemiology and transmission in the United States.
  • List the clinical features of dengue.
  • Explain dengue diagnostic testing for patients with suspected dengue.
  • Describe appropriate treatment for dengue patients according to severity classification.
 

Wednesday, October 21, 2026

Washington State: Updated guidance for novel influenza screening and influenza subtyping


MMWR: Fatal Human Case of HPAI A(H5N5) in a Backyard Flock Owner
 — Washington, November 2025

#19,381

In November of 2025, Washington State reported the first known human infection with avian H5N5; a diagnosis that was delayed - according to an MMWR report - by  `early and repeated negative influenza test results from upper respiratory swab specimens'.

As we've previously discussed, it takes a certain amount of luck for novel flu infections to be detected, properly treated, and then reported to the CDC.  

The problem being that standard rapid influenza tests don't distinguish between seasonal and novel flu strains, and sometimes, repeated swabs of the upper airway can fail to `capture' a deep lung infection for RT-PCR testing. 

In the H5N5 case above, the patient died. In 2024, a Missouri patient was hospitalized with influenza A, and released, before being notified they had H5N1 (see Missouri DHSS: Human H5 bird flu case confirmed in Missouri). In both cases, numerous hospital workers (and others) were unknowingly exposed.

How many novel flu infections go undetected is unknown, although numerous studies suggest it happens more than we think (see JAMA Open: Asymptomatic Human Infections With Avian Influenza A(H5N1) Virus Confirmed by Molecular and Serologic Testing  and  MMWR: Serologic Evidence of Recent Infection with HPAI A(H5) Virus Among Dairy Workers).

No screening system can be expected to catch every case (and many mild cases simply won't seek medical care), but a standardized screening procedure can improve the chances. 

Yesterday King County, Washington published updated guidance for screening for novel influenza, following last week's report of a dairy-exposure infection in Yakima county.  This appears to be a condensed version of guidance published by the WA State Dept. of Health (Provider Alert: Testing and Subtyping for Avian Influenza) published on Oct 9th. 

The emphasis here is on testing patients with ARI (Acute Respiratory Illness) with recent (past 10 days) epidemiologic risk factors (poultry/livestock exposure, raw dairy or animal products, known contact with a human case, etc.). 

It should be noted that this criteria would not have targeted the BC teenager with H5N1, the Missouri case mentioned above, and several others whose source of exposure remains unknown. 

In early 2025, the CDC issued a HAN: Accelerated Subtyping of Influenza A in Hospitalized Patients, requesting that all hospitalized patients with suspected influenza be subtyped within 24 hours.  

Today's guidance appears to back away from that, although the reason behind that isn't stated.  

Based on the CDC's analysis of 72 human cases since 2024, however, it does appear that the vast majority of known cases had some kind of animal exposure. 

I've reproduced the King County Guidance below, followed by a link to the WA State provider update.  I'll have a postscript after the break.


October 20, 2026

Updated guidance for novel influenza screening and influenza subtyping

➜ This health advisory is also available in PDF format (223 KB)

Current situation

Highly pathogenic avian influenza (HPAI or bird flu) continues to circulate among wild birds and other animals in Washington. Although the risk to the general public remains low, clinicians should remain vigilant for possible avian influenza infections in patients with acute respiratory illness (ARI) and epidemiologic risk factors.

Guidance has changed for the 2026-27 influenza season, summarized below.
Actions requested

Identify
  • Test all patients with ARI AND epidemiologic risk factors for influenza and obtain seasonal influenza subtyping for influenza A-positive specimens. Epidemiologic risk factors include the following within 10 days before symptom onset:
    • Close contact with sick or dead animals or their environments, especially birds, wildlife, livestock (including poultry), or domestic animals suspected of HPAI
    • Consumption or handling of raw animal products or parts from potentially infected animals (e.g., raw cow milk or products made with it, raw meat-based pet food)
    • Close contact (within 6 feet) to someone suspected or confirmed to have avian influenza
  • Influenza A subtyping is NOT requested for patients without epidemiologic risk factors, including hospitalized patients. Note this is a change from previous recommendations.
Test
  • Avian influenza testing is available at WA DOH Public Health Laboratories (PHL) with prior approval from Public Health.
  • If seasonal influenza A subtyping is not available through a clinical or commercial lab, the following specimens may be submitted directly to PHL without pre-approval:
    • All influenza A specimens that result as "unsubtypeable" (influenza A positive test but seasonal influenza A subtype was negative or not identifiable)
    • Specimens from hospitalized patients with risk factors for avian influenza, when seasonal influenza subtyping is not available
Notify
  • Immediately report suspected and confirmed cases of novel influenza to Public Health at 206-296-4774, including patients with ARI and identified epidemiologic risk factors. Do not wait for lab confirmation before notifying us. The following are immediately notifiable:
    • All suspected novel influenza, including avian influenza (influenza A H5 or others); a negative influenza PCR does not rule out avian influenza
    • All influenza A specimens that result as "unsubtypeable"

CONTACT


Communicable Diseases Epidemiology and Immunization Section

401 5th Ave, Suite 1250
Seattle, WA 98104

Phone: 206-296-4774
TTY Relay: 711

Fax: 206-296-4803


Three years ago, in UK Novel Flu Surveillance: Quantifying TTD, we looked at a UKHSA report that it would likely take between 3 and 10 weeks before community spread of a novel flu virus would become apparent to authorities, after anywhere between a few dozen to a few thousand community infections

In 2024 the ECDC issued guidance for member nations on Enhanced Influenza Surveillance to Detect Avian Influenza Virus Infections in the EU/EEA During the Inter-Seasonal Period., which cautioned:

Sentinel surveillance systems are important for the monitoring of respiratory viruses in the EU/EEA, but these systems are not designed and are not sufficiently sensitive to identify a newly emerging virus such as avian influenza in the general population early enough for the purpose of implementing control measures in a timely way.

A sobering reminder that, while we comfort ourselves with our current low number of human novel flu detections, we are probably missing some cases. 

Tuesday, October 20, 2026

Washington State Confirms 5 More Dairy Herds Infected With H5N1 (n=8)

 
 Credit Washington State Dept Ag.

#19,380

Not quite 2 weeks ago the USDA/APHIS announced the first detection of H5N1 in dairy cattle in Washington State, which was followed a week later by the first (reportedly mild) human H5N1 infection reported in the U.S. in 2026 (see Washington State Confirms Human Avian Flu Infection).

Details, such as the genotype, how cattle may have been infected, and the exact exposure (apparently, dairy cattle related) of the human case have yet to be released.  On Oct 8th, the USDA stated "APHIS will complete genetic sequencing and announce final results as soon as they are available.", but thus far I've seen nothing published.       

Screenshot taken today, Oct 20th, 2026. 

Three days ago I posted Washington State Confirms 3rd Dairy Herd Infected With H5N1, which was apparently reported on the 15th. Yesterday the USDA and Washington State Department of Agriculture added 5 more herds, all reportedly in Yakima County. 


Other than the above updated dashboards and graphics, I've found no other information on these latest developments. 

As mentioned previously, Washington is one of the few U.S. states that allows the sale of raw milk in grocery stores, natural food markets, food co-ops, and direct-to-consumer farm stores.

While I'm confident that pasteurization effectively kills the H5N1 virus in commercial milk, raw milk (and milk products) are a different matter.  In 2024 and 2025 we saw a number of high profile reports of pets infected with H5N1 via raw milk and/or raw pet food (see Washington State (WSDA) Announces 2 Households with H5N1 Infected Cats Linked to Raw Food).

On Oct 8th, the State of Washington issued this warning:

Dairy product safety

Pasteurization inactivates viruses and bacteria in milk, including HPAI virus, helping ensure the safety of the dairy supply. Infected cows can shed the virus in their milk, making raw milk and other raw dairy products unsafe for consumption. Avoid raw dairy product consumption, and do not allow your pets to consume raw milk or other dairy products, or raw foods such as raw meat.

But given the sotto voce release of information on these recent events, it isn't clear how well that message is getting out.