Showing posts with label Meningitis. Show all posts

Wednesday, December 17, 2014

Criminal Charges Filed In Fungal Meningitis Case

image


# 9456


In early October of 2012 we became aware of a growing medical crisis involving contaminated preservative-free MPA steroid injections distributed by the New England Compounding Center in Framingham, Massachusetts.  In all, more than 700 patients developed infections from these  tainted injections, and more than 60 died.


Among the survivors, many have suffered serious ongoing disability.  I blogged at some length in 2012 and 2013 on this outbreak, including:


CDC Updates On Fungal Meningitis Outbreak
MMWR: Multistate Outbreak Of Fungal Meningitis
CDC/FDA: Multistate Fungal Meningitis Outbreak – Oct 15th
CDC HAN Advisory & Updates On Fungal Meningitis


In late October, in FDA Statement On Conditions Reported At NECC Facility, we saw a report cited the discovery of unopened vials of preservative-free methylprednisolone during an inspection on October 2nd that were observed to have `greenish black foreign matter’ and/or `white filamentous material’ inside.


Additional testing `confirmed the presence of viable microbial growth in 50/50 vials tested’.


On November 2nd, the story grew worse when the CDC released a CDC HAN Advisory: Additional NECC Products Found Contaminated, and again in December the CDC/FDA released a report (see CDC HAN Update On Fungal Meningitis Outbreak )

Laboratory Testing and Results

[12-12-2012] FDA and CDC have identified bacterial and/or fungal contamination in unopened vials of betamethasone, cardioplegia, and triamcinolone solutions distributed and recalled from NECC. These include bacteria known as Bacillus, and fungal species including Aspergillus tubingensis,  Aspergillus fumigatus,  Cladosporium species,and Penicillium species.


While not the first compounding pharmacy-related outbreak, this was certainly the worst. In Revisiting An Earlier Fungal Meningitis Outbreak, we looked at a similar, albeit much smaller, outbreak in 2002 involving a pharmacy in South Carolina.

Today, via Maggie Fox of NBC News, we learn that the Feds have filed a variety of charges (including two with 2nd degree murder) against 14 people involved in the production, distribution, and alleged cover-up of these contaminated products. 

Follow the link to read Maggie’s excellent coverage:

Feds File Murder Charges in Fungal Meningitis Outbreak

By Maggie Fox

The owners and senior officers of a Massachusetts pharmacy that distributed contaminated drugs that killed 64 people have been arrested and two were charged with second degree murder.

Barry Cadden, owner and head pharmacist at the New England Compounding Center (NECC), and other top staffers not only knew their products weren't sterile, but they conspired to cover it up, the U.S. Justice Department says in the indictment.

(Continue . . . )

Thursday, March 28, 2013

CDC Update & Infographic On Fungal Meningitis Case


image


# 7038


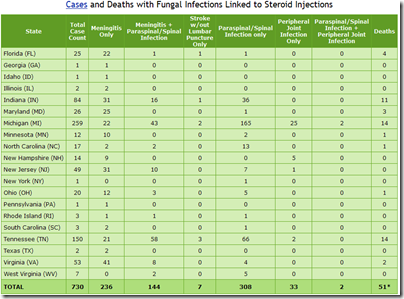
While not commanding the headlines that it did six months ago, the health impacts from last summer’s contaminated injectable steroids continue (see MMWR: Multistate Outbreak Of Fungal Meningitis). 

Since the recall was announced in late September, we’ve learned of more than 50 deaths, nearly 700 still battling infections, with thousands more exposed and potentially still vulnerable to infection.


The latest updates from the CDC (March 25th) are provided below, along with an infographic/timeline of the outbreak.


image 

CDC continues to receive reports of patients presenting with paraspinal/spinal infections (e.g., epidural abscess, phlegmon, discitis, vertebral osteomyelitis, or arachnoiditis at or near the site of injection). These syndromes have occurred in patients with and without evidence of fungal meningitis.


Because these infections are distinct from meningitis and joint infections, CDC will report case counts, as below, to better describe types of infections being identified in patients exposed to a preservative-free methylprednisolone acetate (MPA) injection, with preservative-free MPA that definitely or likely came from one of the following three lots produced by the New England Compounding Center (NECC) [05212012@68, 06292012@26, 08102012@51].

image 

The infographic below provides a good overview of the outbreak.


fungal-meningitis.

Thursday, March 07, 2013

NYC Updates MSM Meningitis Warning

image

Credit NYC Department of Health


# 6989


Last October, in NYC: The Other Meningitis Outbreak, we looked at an early warning issued by the NYC health department to Men who are HIV-infected and who have had intimate contact with another man met through a website, digital application (“app”), or at a bar or party since September 1, 2012 – who may have been exposed to meningitis.


At the time, the New York City Department of Health and Mental Hygiene provided the following recommendation.


Health Department Reccomends Vaccination for HIV-Positive Men at High Risk of Meningitis

The Health Department issued recommendations today for vaccinating against invasive meningococcal disease – commonly known as meningitis – after a spike of cases reported over the past five weeks.


In January we saw an MMWR report (see MMWR: Invasive Meningococcal Disease Among MSM In New York City) and an expansion of vaccination recommendations to include:


. . .  for men, regardless of HIV status, who have had intimate contact with another man that he met through a website, digital application (“App”), or at a bar or party since September 1, 2012 AND live in the following neighborhoods: Bedford-Stuyvesant, Brownsville, Bushwick, Clinton Hill, Crown Heights, Downtown Brooklyn, Dumbo, East New York, Prospect Heights and Williamsburg.


Yesterday, after recording four new cases since the first of the year, NYC issued a new Physician Health Alert (HAN) (PDF) and press release expanding their vaccination recommendations.


First from the HAN notice.


2012 ALERT # 5


UPDATE: Invasive Meningococcal Disease in Men Who Have Sex with Men,Four New Cases Reported in 2013, Expanded Vaccine Recommendations


Please Share this Alert with All Emergency Medicine, Family Medicine, Primary Care Physicians, HIV Specialists, Infectious Disease, and Internal Medicine Staff in Your Facility

  • Four new cases of invasive meningococcal disease have occurred in men who have sex with
    men (MSM) in 2013, bringing the total number of cases to 22.
  • Providers must immediately notify the Department of Health and Mental Hygiene (DOHMH)
    of suspect cases. Do not wait for culture confirmation to report a suspected case.
  • DOHMH has simplified and expanded its vaccine recommendations. Meningococcal vaccine
    should now be offered to:
    • (a) All HIV-infected MSM
    • (b) MSM, regardless of HIV status, who regularly have close or intimate contact with men met through an online website, digital application (“app”), or at a bar or party.


Excerpts from the public press release:


Recent Meningitis Outbreak


March 6, 2013 – The Health Department issued new recommendations today for vaccinating against invasive meningococcal disease – commonly known as meningitis – after an increase in cases.


Vaccinations are now advised for men, regardless of HIV status, who regularly have intimate contact with other men met through a website, digital application (“App”), or at a bar or party. The Health Department also continues to recommend vaccinations for all HIV-positive men who have sex with men. Individuals who are not sure if they meet the criteria are advised to discuss their need for vaccination with their health care providers.


“Meningitis symptoms usually come on quickly, and the disease can be fatal if not treated right away,” said Health Commissioner Dr. Thomas Farley. “Vaccination is the best defense. I urge all men who meet these criteria – regardless of whether they identify as gay – to get vaccinated now and protect themselves from this disease before it is too late.”


Individuals who meet some, but not all, of the criteria are advised to discuss their need for vaccination with their health care provider.


- Read the most recent press release


For more on Meningococcal Meningitis, The New York City Department of Health and Mental Hygiene maintains a FAQ page.


Meningococcal Meningitis


What is invasive meningococcal disease?
Invasive meningococcal disease is a severe infection caused by the bacteria Neisseria meningitidis (meningococcus) that includes both meningitis (infection of the meninges - a thin lining covering the brain and spinal cord) or meningococcemia (infection of the blood). The infection can also occur as pneumonia (an infection of the lungs) or in joints, such as the knees. In 2009, there were 17 cases of invasive meningococcal disease reported among New York City residents (rate of 0.21 cases per 100,000 persons).

Who gets invasive meningococcal disease?
Anyone can get invasive meningococcal disease. Infants < 12 months of age have the highest rates of disease. Clusters of cases and outbreaks do occur but are rare in the United States.
How is invasive meningococcal disease spread?
The meningococcus is spread by direct close contact with nose or throat discharges of an infected person. About eight percent of healthy people carry this particular bacterium in their nose and throat without any signs of illness. Why certain people become ill upon acquiring the organism is not fully understood. Close living quarters, such as in military barracks and dormitories, favor transmission of the organism.
What are the symptoms of invasive meningococcal disease?

Although most people exposed to the meningococcus bacteria do not become seriously ill, some may develop fever, headache, vomiting, stiff neck and a rash. Sometimes the disease can be fatal.

(Continue . . . )


image

The CDC’s webpage on Meningococcal Disease.

Tuesday, March 05, 2013

CDC Update/HAN Message On Fungal Meningitis Outbreak

image Credit FDA


# 6980


Although the rate has slowed, nearly six months after the recall was announced (see CDC Updates On Fungal Meningitis Outbreak), new cases of fungal infection linked to contaminated steroid injections continue to surface around the nation.


image

Credit CDC Multistate Fungal Meningitis Outbreak Investigation


Meningitis and stroke have been among the most serious adverse effects, but for some, the symptoms of fungal infection have been more subtle and have taken months to develop. 


Since these patients already had joint/spinal pain when they received these steroid injections - it isn’t always easy to identify patients who develop pockets of these slow growing organisms.


Yesterday, in addition to posting their weekly update on the outbreak (see above), the CDC released an updated HAN Health Update, advising doctors to remain vigilant in treating patients in their care who may still be at risk of developing infection.


Notice to Clinicians: Continued Vigilance Urged for Fungal Infections among Patients Who Received Contaminated Steroid Injections

Summary

CDC continues to receive new reports of fungal infection among patients who were given injections of contaminated methylprednisolone acetate (MPA) from the New England Compounding Center (NECC) in Framingham, Mass. Most of these recent cases have been localized spinal or paraspinal infections (e.g., epidural abscesses) in patients, although new cases of meningitis or arachnoiditis also have been reported. Because many of these new cases are among patients with minimal symptoms, CDC is re-emphasizing the recommendation for clinicians to remain vigilant for fungal infections, especially in patients with mild or even baseline symptoms, and consider evaluation with magnetic resonance imaging (MRI) if clinically warranted. This Health Alert Network (HAN) notice provides the following:

  • Information about the current status of the outbreak;
  • Recommendations for clinical management and follow-up of exposed patients;
  • Information about new revisions to web-based interim clinical guidance (http://www.cdc.gov/hai/outbreaks/clinicians/guidance_cns.html); and
  • Notice of an upcoming CDC conference call to provide clinicians with additional diagnostic and treatment information.
Status of Fungal Disease Outbreak

As of March 4, 2013, a total of 720 cases, which includes 48 deaths, have been reported in 20 states. Current information about the outbreak, including case counts and distribution by state, and clinician and patient guidance, is available online at http://www.cdc.gov/hai/outbreaks/meningitis.html.

Fungal meningitis, often with a mild clinical presentation, was the predominant clinical syndrome reported among case-patients during the first several weeks of the outbreak (Figure 1). Over the past several months, there has been a marked decrease in reports of fungal meningitis, but CDC continues to receive reports of localized spinal and paraspinal infections, which include epidural abscess, phlegmon, arachnoiditis, and discitis.  Additionally, some of these newly identified case-patients had initially tested negative for signs of a fungal infection (either by lumbar puncture or MRI) and have subsequently developed fungal infection, indicating a prolonged incubation period.

Figure 1

Figure 1: Week of Diagnosis of Case-Patients (n=661) with Meningitis or Spinal/Paraspinal Infection

After the recall of NECC steroid medications on September 26, state and local health departments identified almost 14,000 people in 23 states who were potentially exposed to the implicated MPA; of these, an estimated 11,000 individuals received spinal or paraspinal injections. Through active notification by clinics with assistance from states and CDC in early October, nearly all of these exposed persons were contacted at least once and informed of their risk for fungal infection as a result of receiving injections with contaminated medication.


Despite this and subsequent patient outreach efforts, CDC and public health partners remain concerned about the potential for some exposed patients to have localized fungal infections that have gone unrecognized. These infections may be unrecognized because some patients have not continued to receive close clinical follow-up or because they have not recognized symptoms suggestive of a localized infection, which may be difficult to distinguish from their baseline chronic pain.


As described in CDC’s HAN update on December 20 (http://emergency.cdc.gov/HAN/han00338.asp), MRI testing was done on 128 patients in Michigan, Tennessee, and North Carolina who had no previous evidence of infection and had new or worsening symptoms at or near the site of their spinal or paraspinal injection. Of these, 67 (52%) had findings suggestive of localized infection.  In addition, of 109 different patients reporting persistent but baseline symptoms at or near the site of their spinal or paraspinal injection, 15 (14%) also had abnormal MRI findings suggestive of infection, and 27 (25%) had non-specific enhancement of soft tissue or other paraspinal structures.  The clinical significance of these findings is unclear; however, there is a theoretical risk that failure to diagnose these infections in a timely fashion could result in poor outcomes for patients (e.g., neurologic compromise, osteomyelitis, or progression to meningitis)

Patient and Clinician Recommendations

Early in the outbreak, CDC advised clinicians to closely monitor and evaluate patients who received injections of implicated MPA. Additional guidance was provided in HAN updates issued on November 20 (http://emergency.cdc.gov/HAN/han00335.asp) and December 20 (http://emergency.cdc.gov/HAN/han00338.asp). Because of the possibility that some patients may have unrecognized, localized fungal infections, CDC is re-emphasizing the following recommendations for patients who received a spinal or paraspinal injection with implicated MPA:


Follow the link for Patient and Clinician Recommendations

(Continue . . . )


The CDC’s Health Alert Network (HAN) is designed to ensure that communities, agencies, health care professionals, and the general public are able to receive timely information on important public health issues.


You can sign up for HAN messages, and scores of other CDC and HHS email notifications, by going to the CDC - Quick Subscribe GovDelivery page

Saturday, January 05, 2013

MMWR: Invasive Meningococcal Disease Among MSM In New York City

Meningitis Cases in New York City

Two men standing side by side

Health department is recommending vaccination for certain men at high risk for meningitis. For the latest information, visit the New York City Department of Health and Mental Hygiene.  Photo Credit CDC  Meningococcal Disease


# 6826


Last October, in NYC: The Other Meningitis Outbreak, I wrote about an ongoing outbreak of bacterial meningitis that had been reported in New York City among certain HIV positive men who had sex with other men (MSM).


Six weeks later, after two more infections had come to light, the New York City Health Department issued a statement recommending that certain MSM – regardless of their HIV status -  get the meningitis vaccine.


Health Department Expands Vaccination

Recommendations for Men at Greatest Risk for Contracting Meningitis


Two new cases of meningitis among men who have sex with men were reported over the past five weeks


November 29, 2012 – The Health Department issued new recommendations today for vaccinating against invasive meningococcal disease – commonly known as meningitis – after an increase in cases. Vaccinations are now advised for men, regardless of HIV status, who have had intimate contact with another man that he met through a website, digital application (“App”), or at a bar or party since September 1, 2012 AND live in the following neighborhoods: Bedford-Stuyvesant, Brownsville, Bushwick, Clinton Hill, Crown Heights, Downtown Brooklyn, Dumbo, East New York, Prospect Heights and Williamsburg.

(Continue . . . )


Vaccination can help prevent infection, but does not treat an active infection. A person can be a carrier, and transmit the infection, without falling ill themselves (cite).


Treatment is with antibiotics and steroids, but even with treatment, 10%-15% of patients may die. Severe neurological sequelae may occur as well.


Which brings us to a Notes From The Field report in the most recent MMWR.


Notes from the Field: Serogroup C Invasive Meningococcal Disease Among Men Who Have Sex With Men — New York City, 2010–2012

Weekly

January 4, 2013 / 61(51);1048-1048

On September 27, 2012, the New York City (NYC) Department of Health and Mental Hygiene (DOHMH) alerted health-care providers and the public about 12 cases of invasive serogroup C Neisseria meningitidis disease (SCMD) occurring in NYC since August 2010 among men who have sex with men (MSM). Cases were identified through existing mandatory notifiable disease reporting and classified according to the Council of State and Territorial Epidemiologists case definitions (1). By December 31, 2012, a total of 18 cases had been identified among MSM. For 2012, the incidence rate of invasive meningococcal disease among MSM aged 18–64 years was 12.6 per 100,000 persons, compared with 0.16 among non-MSM males aged 18–64 years. MSM and non-MSM population denominators were obtained from the 2010 NYC Community Health Survey (2) a telephone-based survey of approximately 10,000 NYC residents.


All 18 patients were hospitalized, and five deaths occurred. The age range among patients was 21–59 years (median: 32 years). Nine lived in Brooklyn, four in Manhattan, two in the Bronx, and two in Queens; one was homeless. Nine were black, and four were Hispanic. Ten were infected with human immunodeficiency virus (HIV), including eight of 12 cases reported during 2012. Eleven of 12 isolates were closely related (>85%) by pulsed field gel electrophoresis (3) to a strain from a 2006 SCMD outbreak in Brooklyn (4); the last six out of seven patients' isolates were indistinguishable from each other. At least seven patients had met multiple sexual partners online.


On October 4, 2012, DOHMH recommended administration of meningococcal vaccine to HIV-infected male NYC residents who had intimate contact with any man met online, through a smartphone application, or at a bar or party since September 1, 2012. On November 29, DOHMH expanded its recommendation to HIV-uninfected men with the same high-risk behaviors who reside in areas of Brooklyn where recent cases have clustered. In addition, DOHMH publicized this outbreak among the population at risk through advertising, mass e-mail messages on MSM websites, posters distributed at MSM bars and clubs, and outreach to community leaders and physician's groups.


More information regarding invasive meningococcal disease and this outbreak is available on the CDC and DOHMH websites (5). Public health departments should be alert for cases of SCMD in MSM and should ask SCMD patients about sexual history, travel history (including travel to NYC), and HIV status to help determine if this outbreak is spreading to other juridictions.


For more information, the CDC maintains an extensive website on Meningococcal Disease.


image

Thursday, December 20, 2012

CDC HAN Update On Fungal Meningitis Outbreak

image 

Photo Credit FDA

# 6796


While the number of new meningitis cases linked to contaminated steroid injectables produced by NECC have slowed in recent weeks after their recall in late September, the number of slower-to-develop  paraspinal/spinal & peripheral joint (site of injections) infections continues to rise.


image 


In many cases, the symptoms of fungal infection are subtle - and since these patients (by definition) already had joint/spinal pain when they received these injections - it isn’t always easy to identify patients who develop pockets of these slow growing organisms.


The CDC, in reviewing diagnostic imaging of a number of patients who received these injections, has determined that there may be a substantial number of as-yet unrecognized infections out there. 


So today they have issued a HAN Health Update.


December 20, 2012, 11:55 ET (11:55 AM ET)
CDC HAN-0338-2012-12-20-U-N

Update: Multistate Outbreak of Fungal Infections among Persons Who Received Injections with Contaminated Medication

Summary
New information from diagnostic imaging of patients exposed to contaminated methylprednisolone acetate (MPA1) from the New England Compounding Center (NECC) in Framingham, Mass., demonstrates the need for assertive clinical evaluation of these patients for the possibility of an unrecognized, localized spinal or paraspinal infection. This Health Alert Network (HAN) notice provides updated guidance and information about the ongoing multistate outbreak of fungal infections as follows:

  • CDC and state partners have analyzed new preliminary data based on recent Magnetic Resonance Imaging (MRI) studies among patients who had spinal or paraspinal injection with contaminated MPA from NECC. These findings demonstrate that among patients with no previous evidence of infection, and with new or worsening symptoms at or near the site of their injection, more than 50% had findings suggestive of a localized spinal or paraspinal infection, including epidural abscess, phlegmon, arachnoiditis, discitis, or vertebral osteomyelitis.
  • This new information suggests that some patients who received spinal or paraspinal injections with implicated MPA from NECC may currently have an unrecognized, localized spinal or paraspinal infection.
  • CDC is therefore re-emphasizing the guidance from the November 20 HAN advisory that recommended clinicians remain vigilant for evidence of fungal infection in these patients and use an assertive approach for clinical management and follow-up of these patients. CDC continues to recommend MRI with contrast of the symptomatic area(s) in patients with new or worsening symptoms at or near their injection site following spinal or paraspinal injection of implicated MPA.
  • In addition, CDC is recommending that clinicians should consider obtaining an MRI with contrast of the injection site in patients with persistent but baseline symptoms because the presentation of these spinal or paraspinal infections can be subtle and difficult to distinguish from a patient’s baseline chronic pain.


(Continue . . .)


The CDC’s Health Alert Network (HAN) is designed to ensure that communities, agencies, health care professionals, and the general public are able to receive timely information on important public health issues.


You can sign up for HAN messages, and scores of other CDC and HHS email notifications, by going to the CDC - Quick Subscribe GovDelivery page.


There are 4 types of HAN releases, starting from the highest priority to the lowest.

  • Health Alert - Conveys the highest level of importance; warrants immediate action or attention.
  • Health Advisory - Provides important information for a specific incident or situation; may not require immediate action.
  • Health Update - Provides updated information regarding an incident or situation; unlikely to require immediate action.
  • Info Service -Provides general information that is not necessarily considered to be of an emergent nature.


Complicating matters, last week the FDA updated their list of contaminates detected in injectable drugs produced by this compounding pharmacy.


Laboratory Testing and Results


[12-12-2012] FDA and CDC have identified bacterial and/or fungal contamination in unopened vials of betamethasone, cardioplegia, and triamcinolone solutions distributed and recalled from NECC. These include bacteria known as Bacillus, and fungal species including Aspergillus tubingensis,  Aspergillus fumigatus,  Cladosporium species,and Penicillium species.

Although rare, some of the identified Bacillus species can be human pathogens.  Some of the fungal organisms identified, particularly Aspergillus fumigatus, are known to cause disease in humans.  It is not known how product contamination with these organisms could affect patients clinically.

 image

Tuesday, December 04, 2012

Referral: McKenna On The Steroid-Linked Meningitis Outbreak

image

CDC update 12/3/12


# 6762


Maryn McKenna, writing on her Superbug Blog this morning, has the details of a special briefing provided to her and others from the Association of Health Care Journalists by the CDC on the multi-state meningitis outbreak linked to contaminated steroid injections.


Follow the link to read:


Fungal Meningitis From Injections: Not Even Close To Over

Wednesday, November 14, 2012

CDC Update Of Fungal Meningitis Cases

image


# 6717


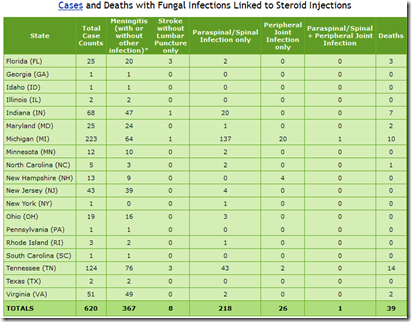
The CDC - which now issues updates on Mondays, Wednesday, and Friday - indicates that 23 new cases of fungal infection from contaminated steroids have been identified since last Friday’s report (Monday was a Federal Holiday).


image

*451 cases of fungal meningitis, stroke due to presumed fungal meningitis, or other central nervous system-related infection meeting the outbreak case definition, plus 10 peripheral joint infections (e.g., knee, hip, shoulder, elbow). No deaths have been associated with peripheral joint infections.


The bulk of these newly identified cases (20) are listed as coming from Michigan, although no details are given.  A quick check of the Michigan Department of Health’s website still shows case counts current as of November 9th.


As of November 9, 2012, Michigan's case count associated with the Centers for Disease Control and Prevention multi-state meningitis investigation is 128 total cases and eight deaths [64 cases of meningitis, eight deaths*, 57 epidural abscess, one stroke and six joint infections].


Since these reports don’t tell us the date of onset of symptoms, we really can’t tell how many of these cases are `new’ in the past couple of weeks, and how many are older, but just now being identified. 


The assumption is that no contaminated steroids were administered to patients after the recall notice was announced in late September.


The danger of developing meningitis is believed greatest during the first six weeks after injection, so there is some hope that the number of new cases will begin to decline soon.


We’ve also seen reports of epidural abscesses and arachnoiditis among some of these patients. These are localized pockets of fungal infection that are slow to grow, difficult to identify, and even more difficult to treat.


The CDC updated their Frequently Asked Questions for Clinicians late last week, with the following information.

Epidural Abscess and Arachnoiditis

There have been media reports of spinal epidural abscesses and arachnoiditis among patients who received treatment for meningitis. What are these conditions and their symptoms?

CDC has received preliminary reports of spinal epidural abscesses and arachnoiditis occurring among a portion of patients undergoing treatment for fungal meningitis due to this outbreak. CDC does not know at this time how many patients developed these disorders or why they occurred.  Both conditions are rare but serious disorders in the general population that require prompt medical attention. 

  • A spinal epidural abscess is characterized by inflammation and a collection of pus around the spine. Spinal epidural abscesses sometimes result in swelling in the affected area (e.g., near the site where contaminated steroid mediation was injected).
    • Common symptoms can include fever, headache, back pain, and neurological problems (e.g., weakness, unusual changes in sensation)
  • Arachnoiditis is a disorder caused by the inflammation of the arachnoid, one of the membranes that surrounds and protects the nerves of the spinal cord. The condition can be caused by irritation from chemicals, infection, or direct injury to the spine.
    • Symptoms can include numbness, tingling, and a characteristic stinging and burning pain in the lower back or legs.  Some people with arachnoiditis may have debilitating muscle cramps, twitches, or spasms.  The condition may also affect the bladder, bowel, and sexual function.  In severe cases, arachnoiditis may cause paralysis of the lower limbs. 
    • For more information about arachnoiditis, see the National Institute of Neurological Disorders and Stroke’s website.


The emergence of these new syndromes linked to fungal tainted steroid injections adds yet another level of uncertainty for those who are waiting to see if they will develop symptoms.


And finally, the head of the embattled pharmacy that created and distributed these steroid products appeared before a congressional committee today, but declined to testify.   This from the Boston Globe.


Pharmacy head pleads Fifth at meningitis outbreak hearing

WASHINGTON Barry Cadden, the owner and director of the specialty pharmacy tied to deadly fungal meningitis outbreak declined to testify Wednesday morning before a congressional committee investigating the matter.

Friday, November 02, 2012

CDC HAN Advisory: Additional NECC Products Found Contaminated

image

# 6690


Last night the CDC – as part of their investigation into the multistate fungal meningitis outbreak linked to contaminated steroid products distributed by the New England Compounding Center (NECC) -  issued a pair of HAN Advisories. 


  • The first, is a notification that two additional products produced by NECC (betamethasone and cardioplegia solution) have tested positive for bacterial contamination.  
  • The second advisory is essentially a HAN version of the FDA’s announcement on Wednesday of a total recall of all Ameridose products.  Ameridose is a a sister company to NECC.


The CDC’s Health Alert Network (HAN) is designed to ensure that communities, agencies, health care professionals, and the general public are able to receive timely information on important public health issues.


You can sign up for HAN messages, and scores of other CDC and HHS email notifications, by going to the CDC - Quick Subscribe GovDelivery page


There are 4 types of HAN releases, starting from the highest priority to the lowest.


  • Health Alert - Conveys the highest level of importance; warrants immediate action or attention.
  • Health Advisory - Provides important information for a specific incident or situation; may not require immediate action.
  • Health Update - Provides updated information regarding an incident or situation; unlikely to require immediate action.
  • Info Service -Provides general information that is not necessarily considered to be of an emergent nature.


Yesterday, the CDC also updated the number of confirmed infections due to these contaminated pharmaceuticals, which now total 377 cases of fungal meningitis, and 9 peripheral joint infections.


image


The following are excerpts from last night’s HAN Advisory on NECC contamination issues.


Contamination Identified in Additional Medical Products from New England Compounding Center

Summary: As part of the ongoing investigation of the multistate outbreak of fungal meningitis and other infections, the Centers for Disease Control and Prevention (CDC) and the Food and Drug Administration (FDA) continue to test medical products from the New England Compounding Center (NECC) in Framingham, Mass.

NECC is the firm that distributed and recalled injectable steroid medications implicated in the current outbreak of fungal meningitis and other infections. CDC and FDA are reporting today that product testing has identified bacterial contamination with several Bacillus species and closely related bacterial organisms in unopened vials of betamethasone and cardioplegia solution that were distributed and later recalled by NECC on October 6, 2012. These bacteria are commonly found in the environment and have been rarely reported as a cause of human disease; it is not known how product contamination with these species might affect patients.

Although clinical infection is possible, CDC has not received reports of laboratory-confirmed cases of infection due to Bacillus or closely related organisms linked to these products. CDC’s recommendations to healthcare providers for diagnosing and treating symptomatic patients who have received NECC products have not changed as a result of these findings. Additional microbial organisms may be identified in recalled NECC products as additional laboratory testing is completed.

<SNIP>

As part of the ongoing investigation, FDA and CDC have been testing various NECC products for evidence of contamination. Laboratory testing at CDC and FDA has found multiple species of Bacillus and closely related bacterial organisms in unopened vials of betamethasone and cardioplegia solution, as shown in the table below.

Medication
Lot number
Microbial contamination

Betamethasone
08202012@141
Paenibacillus pabuli/amolyticus, Bacillus idriensis, Bacillus flexus, Bacillus simplex, Lysinibacillus sp.

Betamethasone
07032012@22
Bacillus niabensis, Bacillus circulans

Betamethasone
07302012@52
Bacillus lentus, Bacillus circulans

Cardioplegia solution
09242012@55
Bacillus halmapalus, Brevibacillus choshinensis

Other cultures for these products, including fungal cultures, are pending.

Recommendations to Healthcare Providers
CDC and FDA have previously advised that healthcare professionals should cease use of any product produced by NECC. On October 15, FDA issued a MedWatch Safety Alert advising clinicians to follow-up with patients who received any injectable NECC product, including betamethasone or cardioplegia solution purchased from or distributed by NECC after May 21, 2012. Clinicians were also requested to report any suspected adverse events following use of these products to
FDA's MedWatch program.


CDC continues to investigate reports of potential infections in patients receiving other NECC products. As of November 1, CDC has received no reports of confirmed infections resulting from injection of any NECC product except those from the three recalled lots of preservative-free methylprednisolone acetate.[1]


CDC’s recommendations to healthcare providers for diagnosing and treating symptomatic patients who have received NECC products have not changed as a result of these findings. CDC continues to recommend routine laboratory and microbiologic tests, including bacterial and fungal cultures, deemed necessary by treating clinicians.


These bacteria have been rarely reported as a cause of human disease. Nevertheless, clinicians should consider these product findings when reviewing laboratory results from patients who have been exposed to a NECC product, since Bacillus and related bacteria are often considered in clinical results to be possible skin contaminants. Physicians should continue to report infections potentially related to NECC products to FDA’s MedWatch and to state health departments.


1. NECC lots of methylprednisolone acetate (PF) 80mg/ml:

  • Methylprednisolone Acetate (PF) 80 mg/ml Injection, Lot #05212012@68, BUD 11/17/2012
  • Methylprednisolone Acetate (PF) 80 mg/ml Injection, Lot #06292012@26, BUD 12/26/2012
  • Methylprednisolone Acetate (PF) 80 mg/ml Injection, Lot #08102012@51, BUD 2/6/2013

Thursday, November 01, 2012

CDC: Laboratory Test Results From Meningitis Outbreak


# 6687


Last night the CDC posted updated laboratory test results from patients - and un-opened vials of methylprednisolone produced by the New England Compounding Center  – as part of their investigation into a multi-state outbreak of fungal meningitis.


The latest numbers from this outbreak, as of 2pm yesterday, are:

image


Lab tests have isolated Exserohilum rostratum in 52 of the 54 patients with CDC laboratory-confirmed fungal meningitis. Tests by the CDC and FDA have also found Exserohilum rostratum in unopened vials from two of the three recalled lots of injectable steroids produced by NECC.   Tests are pending on the third lot.


Here’s the complete CDC Update:


Laboratory Testing and Results from the Outbreak

October 31, 2012 6:00 PM EDT

CDC laboratory-confirmed results found on this page are from three New England Compounding Center (NECC) preservative-free methylprednisolone  acetate (MPA) lots recalled on September 26, 2012.(1)

CDC’s Fungus Reference Laboratory has the capacity and technology to examine fungal isolates under the microscope and to confirm their identification using DNA sequencing methods.

CDC scientist examines microscopic slides showing Exserohilum rostratum (on screen) during the multistate meningitis outbreak.

CDC's Fungus Reference Laboratory has the capacity and technology to examine fungal isolates under the microscope and to confirm their identification using DNA sequencing methods.

  • For the multistate outbreak, the fungus laboratory is working with the Clinical and Environmental Microbiology Branch, Division of Healthcare Quality Promotion, to detect and identify other microbial pathogens. In addition, the Infectious Diseases Pathology Branch, Division of High-Consequence Pathogens and Pathology, is examining tissues from biopsies and autopsy materials.
  • CDC and the states are testing tissue and fluid samples from patients with probable or confirmed fungal infection. CDC scientists are looking to see if the samples contain fungi and other microbial pathogens, and if so, what type.
  • In addition, FDA and CDC are testing vials of NECC preservative-free MPA to see if they contain fungi and other microbial pathogens and if so, what type.

CDC Laboratory Results

As of October 22, 2012, Exserohilum rostratum has been found in clinical specimens for all but two of the 54 patients with CDC laboratory-confirmed fungal meningitis who meet the confirmed case definition.(2)


Tests at CDC and FDA laboratories on the preservative-free MPA vials have confirmed the presence of the same fungus, Exserohilum rostratum, in unopened vials from two of the three recalled lots.(1) Testing on the third lot of preservative-free MPA is ongoing. These laboratory test results strengthen the link between preservative-free MPA vials and the outbreak.


The fungi found in both patients and in recalled vials are common in the environment but were not recognized as a cause of meningitis before this outbreak.

Friday, October 26, 2012

FDA Statement On Conditions Reported At NECC Facility

 image

Photo Credit CDC


# 6669


The FDA has released a report citing the conditions they observed at the New England Compounding Center, the compounding pharmacy who’s steroid products are linked to a multistate fungal meningitis outbreak.


The report cited finding unopened vials of preservative-free methylprednisolone during an inspetion on October 2nd that were observed to have `greenish black foreign matter’ and/or `white filamentous material’ inside.


Additional testing `confirmed the presence of viable microbial growth in 50/50 vials tested’.


It’s an 8-page report, and may be read in its entirety at this link.  Here is the FDA press announcement.


FDA NEWS RELEASE

For Immediate Release: Oct. 26, 2012
Media Inquiries: Sarah Clark-Lynn, 301-796-9110,
sarah.clark-lynn@fda.hhs.gov
Consumer Inquiries: 888-INFO-FDA

FDA reports conditions observed at New England Compounding Center facility

Today, the U.S. Food and Drug Administration released a copy of the FDA Form 483 issued to the New England Compounding Center (NECC). The FDA observed and has since confirmed contaminated products and listed a number of observations regarding conditions in the clean room at NECC’s Framingham, Mass. facility.


The investigators also observed problems with NECC’s ability to maintain its clean room, which is the enclosed space that is designed and maintained to have a controlled environment with low levels of airborne particles and surface contamination. Production of sterile drug products in a properly functioning and maintained clean room reduces the risk of the introduction of microbial contamination into the drug during processing, including filling into its final container.


The FDA issues a 483 at the end of an inspection when the investigators believe that they observed conditions or practices that, in their judgment, may indicate violations of the Federal Food, Drug, and Cosmetic Act, or related regulations.


The 483 does not constitute a final FDA determination that any observation listed on the 483 is a violation of the Federal Food, Drug, and Cosmetic Act or any related regulations.


The FDA considers the 483 along with an Establishment Inspection Report (EIR), prepared by FDA investigators, and any other relevant information, including any responses received by the company. The agency then considers whether further action, if any, is appropriate. The inspection report for NECC has not been completed and is not being shared at this time.


The FDA continues to work closely with the U.S. Centers for Disease Control and Prevention and state partners, including the Massachusetts Board of Registration in Pharmacy, to investigate the outbreak of fungal meningitis among patients who received NECC’s compounded preservative-free methylprednisolone acetate (80mg/ml), an injectable steroid.

For more information: 

# # #

-

-

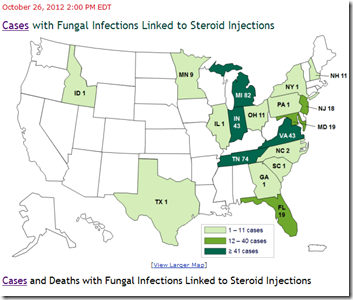
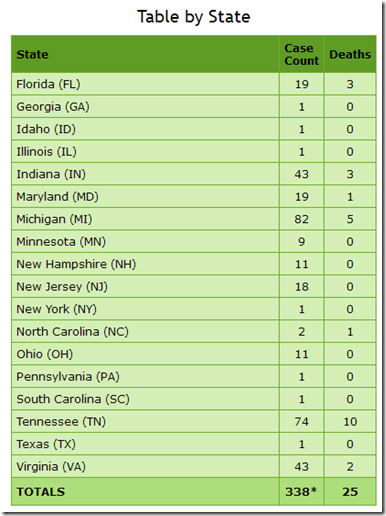
CDC Fungal Meningitis Update – Oct. 26th

image


# 6668


The CDC has posted Friday’s update on the number of cases, and deaths, associated with contaminated steroid injections produced by a Massachusetts compounding pharmacy. 

image


The highest risk period according to the CDC is within the first 6 weeks following injection. Since the suspect lots of steroids were identified and recalled a month ago, it is hoped the number of new cases will begin to decline in the next few weeks.  


That said, no one knows for sure how long before a person can be declared `out of the woods’. 


During a similar incident in 2002, one case did not develop signs of infection until nearly 6 months after exposure (see Revisiting An Earlier Fungal Meningitis Outbreak).


The CDC breaks down today’s numbers:

image

331 cases of fungal meningitis, stroke due to presumed fungal meningitis, or other central nervous system-related infection meeting the outbreak case definition, plus 7 peripheral joint infections (e.g., knee, hip, shoulder, elbow). No deaths have been associated with peripheral joint infections.


For more details on the ongoing investigation, and clinical and patient guidance documents, you can visit the CDC’s website:


Multistate Fungal Meningitis Outbreak Investigation

Wednesday, October 24, 2012

CDC HAN Advisory & Updates On Fungal Meningitis


image

*304 cases of fungal meningitis, stroke due to presumed fungal meningitis, or other central nervous system-related infection meeting the outbreak case definition, plus 4 peripheral joint infections (e.g., knee, hip, shoulder, elbow). No deaths have been associated with peripheral joint infections.


# 6658


Proof this morning that they are burning the midnight oil over at the CDC - as they issued no fewer than seven updates on the fungal meningitis outbreak at 11pm last night – including an updated HAN Advisory.


Six of the seven are guidance documents are designed for practitioners treating exposed, or infected, patients, while the final one is an updated Q&A for patients.


NEW: Health Alert Network (HAN) - Oct 23, 2012 Tuesday, October 23, 2012 11:00 PM


UPDATE: Interim Treatment Guidance for Central Nervous System (CNS) and Parameningeal Infections Associated with Injection of Contaminated Steroid Products Tuesday, October 23, 2012 11:00 PM


UPDATE: Interim Treatment Guidance for Osteoarticular Infections Associated With Injection of Contaminated Steroid Products Tuesday, October 23, 2012 11:00 PM


UPDATE: Interim Guidance for Management of Asymptomatic Persons Exposed to Potentially Contaminated Steroid Products Tuesday, October 23, 2012 11:00 PM


NEW: Guidance on Management of Asymptomatic Patients Who Received Epidural or Paraspinal Injections with Contaminated Steroid Products Tuesday, October 23, 2012 11:00 PM


UPDATE: Frequently Asked Questions for Clinicians: Multistate Fungal Meningitis Outbreak Investigation Tuesday, October 23, 2012 11:00 PM


UPDATE: Frequently Asked Questions for Patients: Multistate Fungal Meningitis Outbreak Investigation Tuesday, October 23, 2012 11:00 PM


The stickiest issue for the CDC, patients, and physicians has been whether to institute some kind of prophylactic anti-fungal treatment in those who have been exposed, but are thus far asymptomatic.


And if the drugs needed were well tolerated, and plentiful in supply, that might be an option.


But the truth is, taking these anti-fungal drugs is not without risk, as they have been linked to liver, heart, and kidney damage. 


Simply put, they are not something you’d want to take for several months, unless you had to.


And there are also concerns that there may not be sufficient supply of these drugs to provide prophylactic treatment to 14,000 patients.


So far, of the 14,000 patients believed exposed, just 2.2 % have developed symptoms.


While that number will likely rise, the CDC believes that patients who have gone more than 42 days since their last injection without showing signs of illness are at a substantially reduced risk of developing meningitis.


Therefore the CDC continues to advise against prophylactic treatment of asymptomatic individuals who may have been exposed.  


This excerpt from last night’s HAN advisory.


October 23, 2012, 22:00 ET (10:00 PM ET)
CDCHAN-00330-2012-10-23-UPD-N

Issuance of Guidance on Management of Asymptomatic Patients Who Received Epidural or Paraspinal Injections with Contaminated Steroid Products

CDC analysis suggests that the period of greatest risk for development of fungal meningitis among patients who received epidural or paraspinal injections with contaminated products1 is during the first 6 weeks (42 days) after injection; therefore, additional monitoring of these patients should be considered. Accordingly, CDC provides guidance for asymptomatic patients who received epidural or paraspinal injections with contaminated steroid product1 within the last 6 weeks (42 days), and those who received such products longer than 6 weeks (42 days) ago. For specific details about the updated guidance, see Guidance on Management of Asymptomatic Patients Who Received Epidural or Paraspinal Injections with Contaminated Steroid Products.


As stated above, CDC does not recommend initiation of antifungal treatment in the absence of diagnostic test results indicating fungal meningitis in exposed patients who are asymptomatic. Currently available data do not suggest an added benefit to this approach in comparison to the strategies outlined in the updated guidance, and patients may experience serious adverse drug events associated with treatment.

(Continue . . . )


Watchful waiting is always difficult, particularly when you are dealing with a potentially fatal condition. But sometimes it really is the lesser of two evils.


Patients who go more than 42 days without developing symptoms are believed to be at reduced risk of illness - but as we saw last week (see Revisiting An Earlier Fungal Meningitis Outbreak) during a similar outbreak 10 years ago in South Carolina - infections cropped up as much as six months post-exposure.


All of which means that this story, and the ordeal for those exposed, isn’t likely to be over anytime soon.

Monday, October 22, 2012

CDC Fungal Meningitis Update – Oct 22nd

image

# 6652


While there are no additions or changes to guidance documents posted on the CDC’s Meningitis website today, the CDC has updated the number of cases, and deaths, associated with the Multistate Fungal Meningitis outbreak.

 image


image

*294 cases of fungal meningitis, stroke due to presumed fungal meningitis, or other central nervous system-related infection meeting the outbreak case definition, plus 3 peripheral joint infections (e.g., knee, hip, shoulder, elbow). No deaths have been associated with peripheral joint infections.


Numbers are changing by the hour, as evidenced by this press release from the state of Florida earlier today adding another case to their total (n=18), a 55 year old man who received treatment at pain clinic in Escambia county.  This from the Florida DOH.


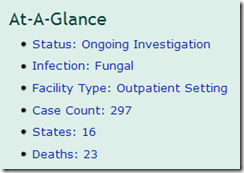
10.22.12 - Florida Fungal Meningitis Cases Total Eighteen


A finally, as you might expect - with 23 deaths and hundreds of serious injuries - lawsuits are being filed on behalf of many who received these injections. 


For now, the compounding pharmacy that shipped the injectable steroids (NECC) is being named as the sole defendant, but others may be included later.


This from the Wall Street Journal.


Lawsuits Mount as Meningitis Deaths Rise

By THOMAS M. BURTON

The compounding pharmacy at the center of a deadly meningitis outbreak is facing a wave of lawsuits from patients who received steroid injections made by the pharmacy.


At least 10 lawsuits, including one seeking class action status, have been filed against the New England Compounding Center of Framingham, Mass. Scores more plaintiffs have retained attorneys to commence litigation.

(Continue. . . )

Friday, October 19, 2012

CDC Fungal Meningitis Update – Oct 19th

image


# 6648


The latest case counts have been posted by the CDC, and today they are reporting 14 additional cases, and another fatality.


image 


*268 cases of fungal meningitis, stroke due to presumed fungal meningitis, or other central nervous system-related infection meeting the outbreak case definition, plus 3 peripheral joint infections (e.g., knee, hip, shoulder, elbow). No deaths have been associated with peripheral joint infections.


The CDC has also updated some guidance documents since yesterday’s case count, and has posted the audio of Tuesday’s COCA (Clinician Outreach and Communication Activity) call on the outbreak.


The COCA call featured briefings by and Q&A with:

Multistate Fungal Meningitis Outbreak Investigation Update: Information and Guidance for Clinicians

Presenter(s):

Melissa K. Schaefer, MD
Medical Officer
Division of Healthcare Quality Promotion
National Center for Emerging and Zoonotic Infectious Diseases
Centers for Disease and Control and Prevention

Tom Chiller, MD, MPH
Medical Epidemiologist
Division of Foodborne, Waterborne & Environmental Diseases
National Center for Emerging and Zoonotic Infectious Diseases
Centers for Disease and Control and Prevention

Peter G. Pappas, MD
Professor of Medicine
Division of Infectious Disease
Department of Medicine
University of Alabama at Birmingham 

Overview:

The Centers for Disease Control and Prevention (CDC) and the Food and Drug Administration (FDA) continue to work closely with state public health departments on a multistate investigation of fungal meningitis among patients who received an epidural steroid injection. These cases are associated with a potentially contaminated steroid medication prepared by New England Compounding Center (NECC), located in Framingham, Mass. During this COCA Call, subject matter experts will provide updates to the current epidemiology of the outbreak, describe clinical presentation and features of fungal meningitis, and review CDC’s recommended treatment guidance.


AUDIO File and TRANSCRIPT available at this link.